

Long-Term Care Hospitals: A Case Study in Waste

Issue Summary
The post-acute care sector provides patients with rehabilitation services following an acute hospital stay. An administrative carve-out in the 1980s resulted in the creation of 40 long-term care hospitals (LTCHs) that were paid differently (and more generously) than other types of post-acute care providers. Since then, the number of LTCHs has expanded dramatically and reached 400 (mostly for-profit) facilities by 2014. LTCHs are a particularly expensive place to receive post-acute care. On average, admission to a long-term care hospital raises post-acute care spending by the Medicare fee-for-service program by approximately $30,000 per admission relative to alternative settings for care delivery (Einav et al. 2019). Patients discharged to an LTCH also owe more money out of pocket, and do not spend less time in institutional care or have lower mortality than if they were discharged to other settings. Taken together, the evidence indicates that Medicare could save roughly $4 billion per year (based on 2017 data) with no harm to patients by not allowing for discharge to LTCHs or by paying them on par with how other post-acute care providers are reimbursed.
Policy Recommendation
Policy makers should eliminate the administratively created concept of LTCHs and have the Medicare program reimburse those facilities on par with how skilled nursing facilities are paid.
Potential Savings
$4 billion per year in spending (based on 2017 data) on traditional Medicare beneficiaries (1% of traditional Medicare spending).
Background
The post-acute care sector provides patients with rehabilitation services following an acute hospital stay. It includes both facility-based care—care in skilled nursing facilities (SNFs), inpatient rehabilitation facilities (IRFs), and long-term care hospitals (LTCHs)—and home-based care provided by home health agencies (HHAs). Within the post-acute care landscape, LTCHs generally provide the most intensive care, SNFs and IRFs provide intermediate levels of care, and HHAs provide the least intensive care.
The Medicare fee-for-service program spends approximately $60 billion per year on post-acute medical services (MedPAC 2019a). This is approximately 15% of the $413 billion in total Traditional Medicare (hereafter, “Medicare”) spending in 2018 (Boards of Trustees for Medicare 2019) and about 5% more than the much-studied Medicare Part D program spending on Traditional Medicare beneficiaries (MedPAC 2019a). Medicare spending on post-acute care grew one percentage point faster per year than overall Medicare spending between 2001 and 2017, and more than doubled over this period (Boards of Trustees for Medicare 2002, 2018; MedPAC 2016, 2019a). A recent Institute of Medicine report found that, despite accounting for only 16% of Medicare spending, post-acute care contributed to a striking 73% of the unexplained geographic variation in Medicare spending (IOM 2013), suggesting that there may be inefficiency in the sector.
Figure 1: LTCH Facilities Over Time
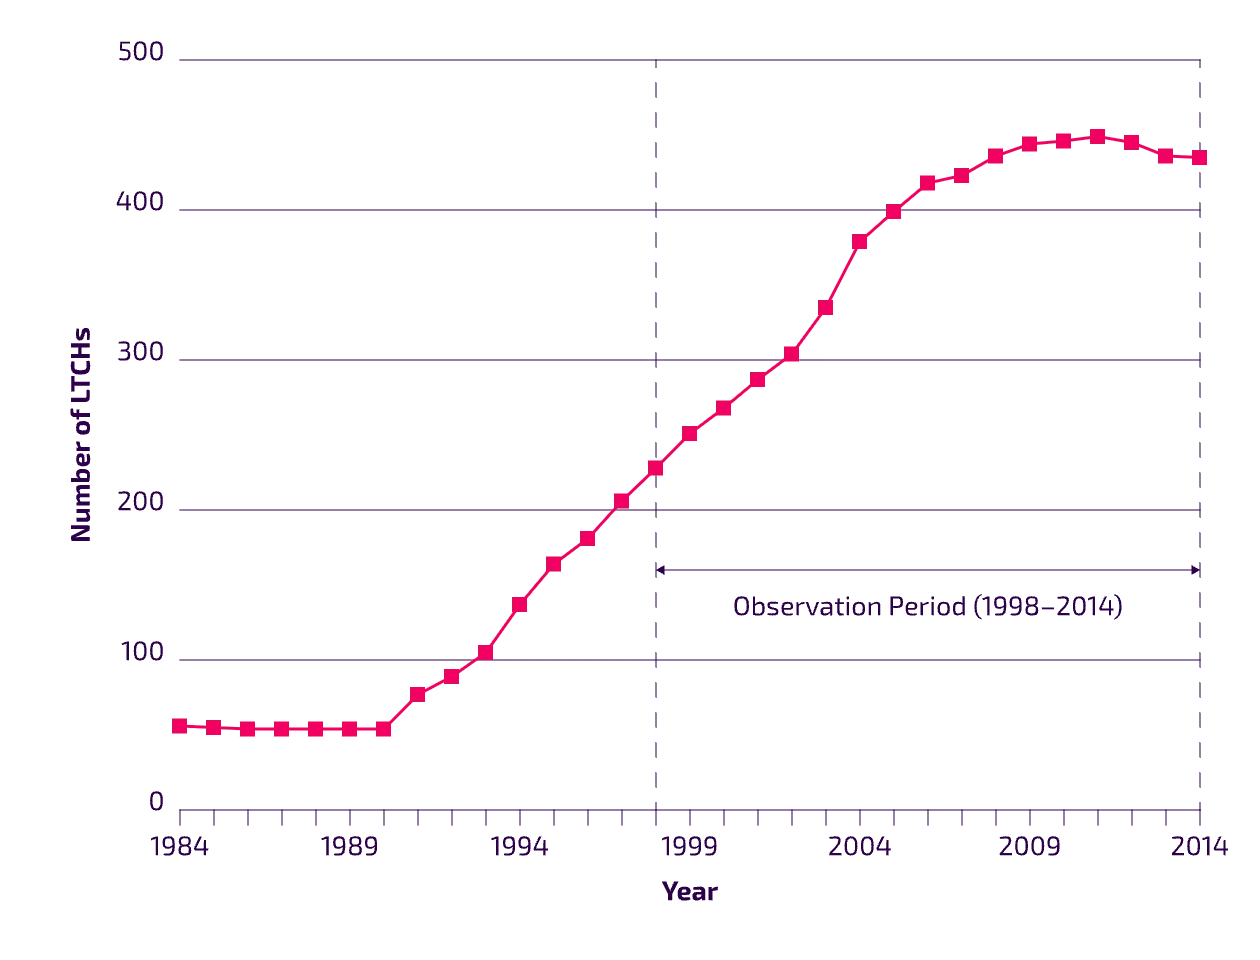
LTCHs are not clinically distinct from other types of post-acute care providers. Instead, they are an administrative concept, born out of legislation in the early 1980s designed to protect 40 chronic disease hospitals from the new Medicare Prospective Payment System introduced in 1983. There is no analogous type of care provider in other industrialized countries.
Since 1982, there has been rapid growth in the LTCH sector. In 2017, LTCHs accounted for about 4% of discharges to facility-based post-acute care facilities and about 11% of facility-based post-acute care spending (MedPAC 2019a). Despite attempts to rein in the sector, the LTCH industry, which started as a legislative carve-out, expanded from 40 facilities to over 400 by 2014, and in 2017 accounted for $4.5 billion in annual Medicare spending (MedPAC 2019b; see Figure 1). The vast majority of LTCHs are for-profit facilities.
Evidence Base
LTCHs are a particularly expensive location to receive post-acute care but deliver no measurable benefits to patients. To estimate the impact of LTCHs on Medicare spending and patient outcomes, researchers examined how patients’ care patterns change when an LTCH enters a market (Einav et al. 2018). When an LTCH first opens in a market there is, not surprisingly, a marked increase in the rate of patients being discharged from an acute care hospital to an LTCH. The research estimates that this discharge to an LTCH increases net Medicare spending by about $30,000. This increase, the researchers find, is because care in LTCHs mostly substitutes for care that would—in the absence of an available LTCH—be delivered by an SNF; these are the most common forms of facility-based post-acute care and are reimbursed approximately $1,000 less per day to SNFs than LTCHs by the Medicare program.
In addition, discharge to LTCHs reduces average length of stay in the originating acute care hospital by over eight days (Einav et al. 2018). This suggests that LTCHs, in some cases, provide care to patients that cannot (at least initially) be provided by SNFs. However, since acute care hospitals are paid a lump sum per patient that is (largely) independent of length of stay, the reduction in length of stay does not result in any savings to Medicare.
Despite dramatically higher spending from being discharged to an LTCH, there is no evidence of benefits to patients. Patients discharged to an LTCH owe more money out of pocket, and they do not spend any less time in institutional care or experience lower mortality. These results hold not only on average, but also when examining the subset of patients who are sickest or most likely to be discharged to LTCHs. This suggests that, in most cases, patients who are discharged to LTCHs can fare just as well through some combination of longer stays in acute care hospitals and discharge to an SNF instead. Taken together, these findings indicate that Medicare could save roughly $3.85 billion per year (based on 2017 spending) with no measurable harm to patients by not allowing for discharge to LTCHs (Einav et al. 2019).
Policy Recommendation
The policy response to address this inefficiency is straightforward: policy makers should eliminate the administratively created concept of LTCHs as institutions with their own reimbursement schedule—and reimburse them instead like SNFs.
Potential Savings
The policy recommendation would save $3.85 billion in Medicare spending per year—relative to $4.5 billion in 2017 total LTCH spending (MedPAC 2016, 2019b)—with no measurable harm to patients. The savings would come primarily from the lower Medicare reimbursement rates for SNFs—where most patients who are currently discharged to LTCHs would otherwise go. In addition to saving $3.85 billion in Medicare spending per year with no harm to patients, eliminating LTCHs would reduce by 10% the unexplained geographic variation in Medicare spending.
Addendum
This addendum was prepared by the Health Care Affordability Lab at Yale.
The original brief proposes eliminating the separate Medicare payment category for long-term care hospitals (LTCHs), arguing that patients can receive comparable care at skilled nursing facilities (SNFs) at a lower cost to Medicare. While this hasn’t been done, federal policymakers have advanced site-neutral payment for certain LTCH stays. Under the Pathway for SGR Reform Act of 2013, Medicare pays a site-neutral rate for LTCH stays that do not meet high-acuity criteria—the lower of the standard inpatient (IPPS) rate or 100% of the stay’s cost—while high-acuity stays keep the standard LTCH rate (MedPAC 2025). During the COVID-19 pandemic, the CARES Act temporarily waived site-neutrality for cases admitted during the public health emergency and paid those LTCH stays the standard LTCH PPS rate (CRS 2020). Recently proposed bills, such as the Patient Access to LTCH Care Act and the STAR Act, have sought to limit LTCH site-neutrality by extending the standard LTCH rate to more types of stays. Since the site-neutral rate took effect, the LTCH sector has contracted—from about 400 facilities and $4.5 billion in Medicare spending in 2017 (MedPAC 2019) to 330 facilities and $3 billion in fiscal year 2023 (MedPAC 2025). That contraction offers a real-world test of the brief’s central premise: if LTCH patients can receive comparable care at lower cost elsewhere, shrinking LTCH access should reduce Medicare spending without worsening outcomes.
Law et al. (2023) examines how LTCH closures between 2012 and 2018 have affected spending and patient outcomes. The authors apply a difference-in-differences approach to estimate the effect of closure on outcomes for roughly 8,400 Medicare patients who received prolonged mechanical ventilation for respiratory failure. The study compares outcomes among 45 hospitals that had relied on a since-closed LTCH with 45 matched control hospitals. LTCH closure was associated with fewer transfers to LTCHs and lower overall spending, with no statistically significant change in patient mortality, length of stay, or institution-free days. Among the sicker subgroup of patients who also received a tracheostomy, LTCH closure was associated with more transfers to SNFs, shorter hospital stays, and more do-not-resuscitate orders—yet no change in mortality rates. On the outcomes the study could measure, this suggests that patients who would otherwise have been discharged to LTCHs were not left worse off by their absence, while overall spending decreased.



More Briefs
$12-$24B
Expanding Site-Neutral Payments in Medicare and Addressing Anticompetitive Vertical Integration of Physicians
