

Expanding Kidney Exchange

Issue Summary
Kidney exchange enables transplants for patients who have a willing live but incompatible donor by arranging swaps and chains with other patient-donor pairs. Each transplant improves the quality and length of a patient’s life while saving several hundred thousand dollars of expensive dialysis treatment over the remaining length of a patient’s life. Recent research has documented that legal and economic barriers in the kidney exchange market keep this mode of transplantation from reaching its full potential. Barriers identified include financial disincentives that limit participation by transplant centers in kidney exchange, poor coordination between kidney exchange platforms and the kidney transplant waiting list, and the untapped potential of coordinating with other countries. Policies aimed at reducing these barriers and improving coordination can create several thousand more transplants per year. These reforms can reduce Medicare spending on kidney failure—which currently costs the taxpayer approximately $36 billion each year (roughly 1% of the national health care expenditure)—while simultaneously improving health outcomes.
Policy Recommendation
This brief discusses three specific proposals for expanding kidney exchange. First, policy makers should eliminate financial disincentives for participating in kidney exchange platforms by including medical and administrative costs specific to kidney exchange in reimbursements from the Medicare program. Second, policy makers should direct the federal contractor UNOS (United Network for Organ Sharing) to allow kidney exchange chains to be initiated by deceased donors. Third, Medicare should pay for the costs of a global kidney exchange that allows exchanges involving patients in different nations.
Potential Savings
Each additional transplant facilitated by kidney exchange saves approximately $146,000 per transplanted Medicare patient (Held et al. 2016) and more for a privately insured patient. If the three proposals combined resulted in 5,000 additional transplants annually, overall savings would be $730 million annually, representing 0.1% of the annual Medicare budget. Moreover, the economic value of each transplant is estimated to be $1.1 million, resulting in $5.5 billion in general economic gains from 5,000 additional transplants.
Background
End-stage renal disease (ESRD) directly impacts more than half a million Americans. Most of the costs of ESRD are borne by the Medicare program and account for approximately 7% of its overall budget. The preferred treatment for ESRD is kidney transplant. Unfortunately, there is a severe shortage of organs available for transplantation. As a result, the bulk of the money the Medicare program spends on ESRD goes toward dialysis (a substitute treatment for kidney transplant).
In 2019, about 40,000 patients were added to the donor waiting list, while just under 17,000 patients were transplanted using organs from deceased donors and 6,900 received transplants from living donors. As a result, there are approximately 90,000 patients on the kidney waiting list, and approximately 8,000 die annually or become too sick to transplant.
Individuals with ESRD who cannot be transplanted require kidney dialysis—a treatment that filters toxins from the blood outside of the body in lieu of relying on the kidneys. Dialysis is inconvenient and debilitating for patients and hugely costly. Therefore, in addition to increasing quality of life and life expectancy, each transplantation saves approximately $146,000 per Medicare beneficiary. Moreover, Held et al. (2016) estimate that each kidney transplant generates $1.1 million in economic value.
This brief outlines three specific proposals to expand the availability of transplanted kidneys in the US.
Kidney Exchanges
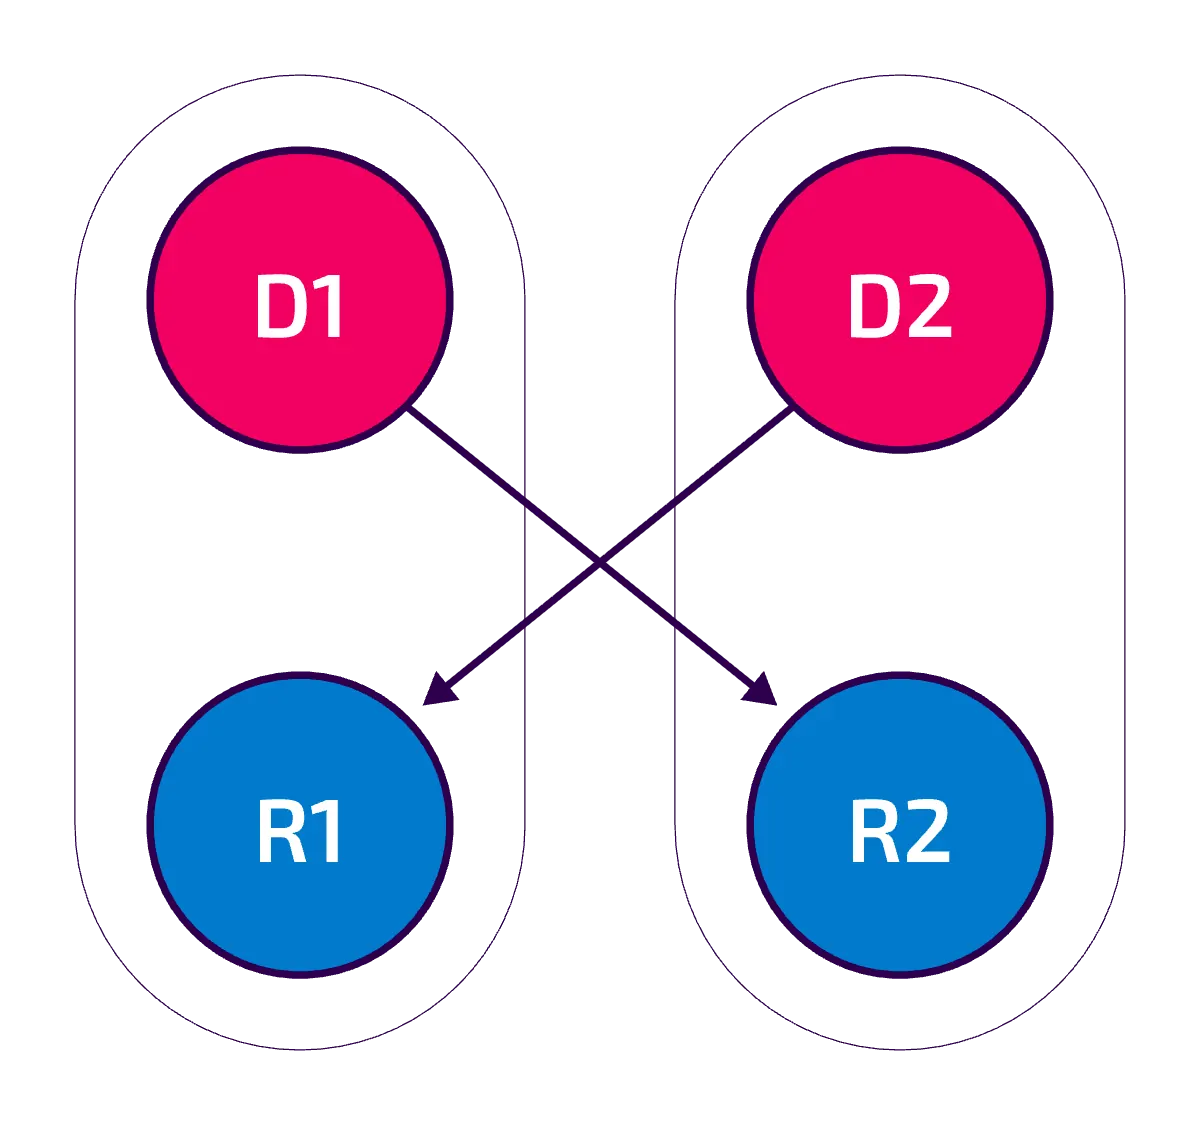
Despite the shortage of organs from deceased donors, there are many patients with kidney failure who have a friend or a loved one who is willing and able to donate one of their kidneys but cannot do so because they are not biologically compatible. One solution in such situations is to perform a kidney exchange, in which two or more incompatible patient-donor pairs exchange kidneys, with each patient in the exchange receiving a compatible kidney from another patient’s donor. Figure 1 illustrates the simplest form of kidney exchange: a two-way swap.
Figure 1: Exchange between two incompatible patient-donor pairs, (D1,R1) and (D1,R2).
More recently, donor chains that take advantage of healthy but incompatible donors have emerged. A donor chain is kicked off by a non-directed donor (either deceased or living) who donates an organ to a recipient with an available, healthy donor who is not a match but is willing to donate their kidney to another recipient with an incompatible willing donor. These chains can involve large numbers of donors. For example, in 2015, there was a 68-person donor chain (34 donors and 34 recipients) that involved kidney transplants at 26 hospitals nationwide. Donor chains represent an opportunity to substantially increase the scale of donations in the US.
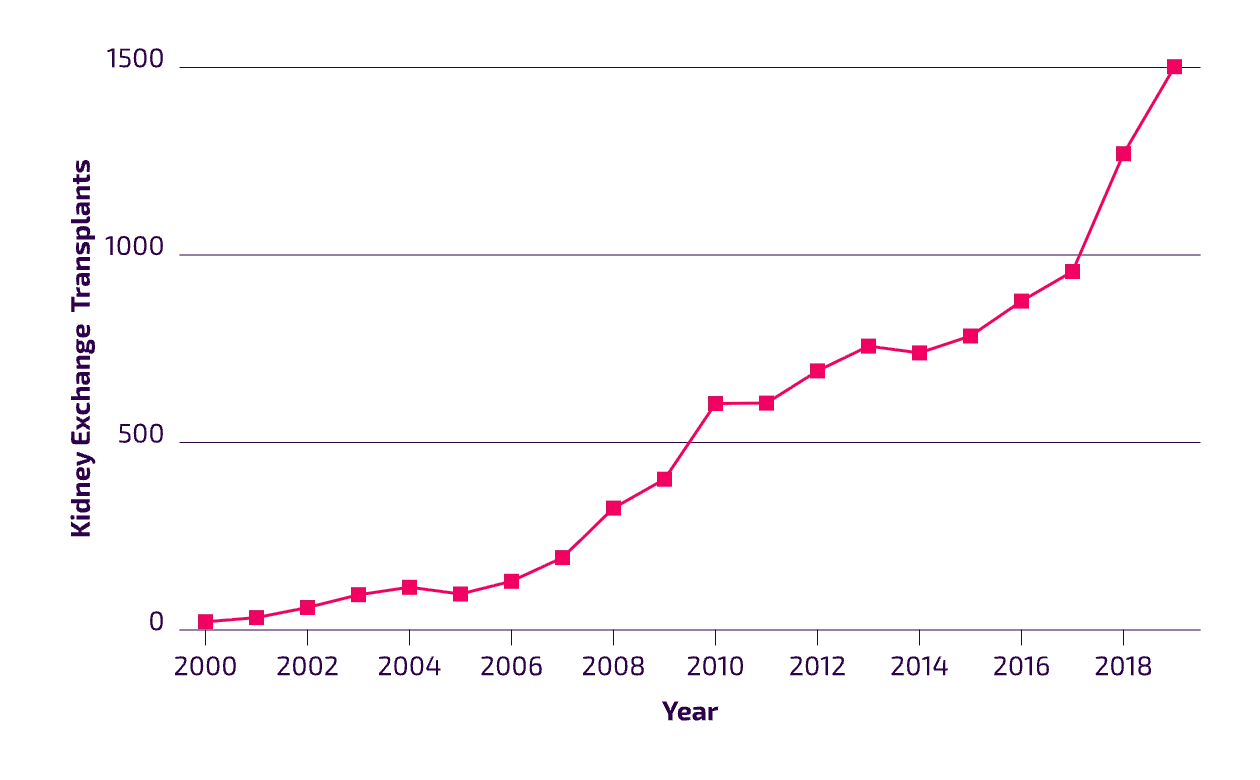
There are kidney exchange platforms in the US that match donor-recipient pairs. On these exchange platforms, patients with a willing but incompatible donor are paired with other donor-recipient pairs. Figure 2 shows that kidney exchange transplants have grown rapidly in the last two decades. At present, there are approximately 1,500 transplants enabled by formalized exchanges annually in the US.
Figure 2: Kidney Exchange Transplants in the US
Unfortunately, while many have benefited from kidney exchange, this mode of transplantation has not reached its full potential. There are several barriers that keep kidney exchange from doing so. This brief describes three such barriers and proposes specific policy solutions.
Policy Recommendation
Reimbursing Costs of Kidney Exchange
There are costs to running kidney exchanges and costs to hospitals for participating in exchanges. While hospitals get monetary benefits from performing transplants, they do not benefit monetarily from participating on an exchange platform. These costs are often cited by hospitals as barriers to participation (Ellison 2014; American Society of Transplant Surgeons 2016). These additional uncompensated costs result in a fragmented and inefficient kidney exchange landscape. The cost, although small relative to the value of additional transplants, discourages hospitals from referring their patients to large kidney exchange programs because they represent a large fraction of hospital profits from kidney transplantation. As a result, the kidney exchange market is highly fragmented—many hospitals only perform kidney exchanges amongst their own donors and patients, and many small hospitals do not participate in kidney exchanges at all.
This barrier to participation is important because the largest kidney exchange platforms, such as the National Kidney Registry (NKR), the Alliance for Paired Kidney Donation (APD), and UNOS, are able to utilize patient-donor pairs that are interested in kidney exchange to set up long chains and swaps much better than single centers. These gains are primarily due to the fact that having many patients and donors on a single platform allows these programs to find rare matches that are not available to a small transplant center. In fact, estimates in Agarwal et al. (2019) suggest that a medium-sized hospital can only transplant about 20% of its patient-donor pairs while a large platform can transplant close to half of its patients and donors.
To solve this problem, the Medicare program should reimburse providers’ costs for participating in kidney exchanges and fund kidney exchange platforms. The best estimates suggest that these costs average $30,000 per transplant. Based on estimates in Agarwal et al. (2019), this policy can increase the number of kidney exchange transplants by upwards of 30% per year or 450 additional transplants per year. This is a substantial increase relative to the 1,500 transplants currently enabled annually by formalized exchanges in the US. Improving this policy will result in generating $500 million in economic value and approximately $66 million in cost savings (based on Medicare spending; more if private insurance).
Instructing UNOS to Initiate Kidney Chains from Deceased Donors
Most kidney exchange transplants on large platforms are performed through chains—links of multiple donor pairs. These chains are initiated by a non-directed donor who does not have a specific patient with whom he or she registers for kidney exchange. The donor related to the patient who receives this kidney can then donate to the next patient, and this chain can continue until, finally, a patient who does not have a related donor receives a kidney. These transplants can occur in sequence, separated by several days or weeks. In large kidney exchange platforms, the median kidney chain involves about five transplants, with many chains facilitating more than twice as many.
While chains are an important part of kidney exchange, the number of chains that can be initiated is severely limited by the number of non-directed donors. Even in the largest kidney exchange platform, only 15% of the donors are non-directed.
We propose that policy makers instruct UNOS to implement the suggestion of Melcher et al. (2016) by first attempting to use deceased donors to initiate kidney chains. Under this proposal, a kidney from a deceased donor would be transplanted to a patient registered at any one of the large multi-hospital kidney exchange platforms. It would be necessary for this patient to be paired with a living donor who is willing to continue the chain. The chain could then enable several transplants. Finally, the kidney from the last donor would be transplanted to a patient on the deceased donor list in order to make sure that the total number of kidneys available to deceased donors is not reduced. In fact, patients waiting for a deceased donor kidney would instead receive a transplant from a living donor, which is typically associated with better health outcomes. Balance on blood types can also be enforced.
We expect that many patients with related living donors should be willing to participate in this program. Many patients in kidney exchange programs have low odds of receiving a transplant because they are highly immunologically sensitive and a hard-to-match blood type. For these patients, priority in the much larger pool of deceased donors can be very useful.
But even with very low participation rates, this change can make a large impact on kidney exchange. In 2019, there were approximately 17,000 kidney transplants from deceased donors. Each donor provided to a chain enables approximately two extra transplants that would otherwise not have taken place (see Agarwal et al. 2019). This number is less than the average chain length because some patients transplanted through a chain would have otherwise received a transplant through a kidney swap.
Therefore, the number of transplants conducted through kidney exchange will more than double if only 5% of deceased donors can be used to initiate chains. For context, the cost savings from an additional 1,700 transplants per year accumulate to approximately $250 million annually, and the economic value of these additional transplants is estimated to be over $1.9 billion.
Paying for Global Kidney Exchange
In the United States, patients who have a compatible living donor are typically able to pay for a direct kidney transplant through the Medicare End-Stage Renal Disease program. However, in many parts of the world, patients with compatible donors who are not able to afford the costs of a transplant do not have a public health care system to rely on. Hence, a financial barrier limits worldwide kidney transplants.
Global kidney exchange is a solution that benefits both patients and donors in the United States and abroad. Bozek et al. (2018) describe the first global kidney exchange chain. In this chain, a Filipino patient-donor pair who could not afford transplantation in the Philippines was brought to the United States and transplanted through a kidney exchange platform. The costs of transplanting the Filipino pair were paid for by the US health care system, and escrow money was set aside to take care of the pair’s follow-up treatment.
Even though the US health care system pays for the transplant of the patient-donor pair from abroad, there are still large cost savings. In the US kidney exchange system, patients whose immune systems are highly sensitized to human proteins and are not compatible with their related living donor have low odds of receiving a living donor transplant. Patient-donor pairs that can be brought in from the rest of the world can be chosen to match these patients. Indeed, the chain involving the Filipino patient-donor pair described above resulted in transplants to 11 patients in total. The Filipino patient received a kidney from a donor in Georgia, and the Filipino donor donated to an American patient in Minnesota who was hard to match with a donor. The donor of the patient from Minnesota continued the chain by donating to a patient in Seattle. The chain continued to result in many transplants.
Our proposal is that policy makers direct Medicare to cover the costs of global kidney exchange. Nikzad et al. (2017) conducted a detailed analysis of the financing arrangements that would be necessary and the cost savings from such a program. If this program generated an additional 2,000 transplants annually, this would result in savings of approximately $300 million with an economic value of $2.2 billion.
Addendum
This addendum was prepared by the Health Care Affordability Lab at Yale.
The lack of kidneys available for transplant remains a major problem in the United States. As of the end of 2023, over 831,000 people were living with end-stage kidney disease—an all-time high—and about 67% relied on dialysis (NIDDK USRDS 2025). Dialysis also remains far more expensive than transplantation. In 2023, Medicare fee-for-service spending averaged $103,127 a year for each patient receiving in-center hemodialysis, the most common form of dialysis, compared with $44,645 a year for a patient living with a functioning kidney transplant (Figure 9.10, NIDDK USRDS 2025).
Matching donors to patients also remains difficult. Many patients are "highly sensitized," meaning their immune systems reject all but a small fraction of donor kidneys, and others have tissue-type mismatches even when blood types align. A larger, more diverse pool of participants improves the odds for these hard-to-match patients.
Since the brief's publication, further research has strengthened the case for the solutions it proposed. First, cost remains a central barrier to participation: in a 2024 national survey of U.S. transplant programs, cost was among the top reasons centers gave for staying out of kidney exchange (Lentine et al. 2026), reinforcing the brief's case that expanding Medicare reimbursement would raise the supply of transplants.
A broader payment reform is separately reshaping the financial incentives hospitals face around transplantation. The Increasing Organ Transplant Access (IOTA) Model, a six-year mandatory Medicare model that began in July 2025, rewards kidney transplant centers for higher transplant volume, accepting more offered deceased-donor kidneys, and maintaining good post-transplant outcomes. The number of transplants accounts for 60% of a hospital's score. Hospitals that score well earn a bonus for each Medicare kidney transplant, while those that score poorly owe money back. IOTA does not reimburse the exchange-specific participation costs the brief targets, but it marks a federal move to tie hospital payment to transplant activity.
Second, allowing deceased-donor kidneys to start exchange chains would expand the pool of possible matches. The proposal was initially circulated for public comment in 2017 but remains under OPTN committee review. Using U.S. data from 2016–2017, a simulation study by Wang et al. (2022) found that devoting fewer than 3% of deceased-donor kidneys to initiating chains could add up to 290 transplants a year—with hard-to-match patients, including highly sensitized and type O candidates, benefiting as well. A 2023 law has since ended UNOS's role as sole contractor for the national transplant network, so the brief's call to direct UNOS now falls to the OPTN and its contractor.
A 2025 study using French administrative data also finds that integrating deceased-donor kidneys into the exchange and loosening the exchange's timing rules—so that a donor and recipient need not give and receive at the same time—could sharply reduce waiting times without disadvantaging patients already waiting for a deceased-donor kidney (Akbarpour et al. 2025).
Third, international exchange has begun to show concrete gains for U.S. patients. Nikzad et al. (2021) refine the original global-exchange idea in a way that addresses two common objections: rather than bringing foreign pairs into the U.S. exchange, the chain begins in the middle-income country—building transplant activity there—with only the final donor traveling to donate to a U.S. patient. It can also be financed by private and self-insured payers out of dialysis savings, without the Medicare legislative change the original proposal would require.
Early, preliminary results are consistent with this potential: between 2015 and March 2024, Global Kidney Exchange delivered living-donor transplants to 21 international patients and 42 U.S. patients (Rees et al. 2024), clearing immunologic and financial barriers. Transplanting those 42 Americans saved U.S. payers an estimated $8–12 million from dialysis, and international recipients have shown 100% three-year survival.





More Briefs
$12-$24B
Expanding Site-Neutral Payments in Medicare and Addressing Anticompetitive Vertical Integration of Physicians
