

Removing All Financial Disincentives to Living Kidney Donation

Issue Summary
An estimated 37 million Americans suffer from chronic kidney disease (CKD) and about 726,000 have End Stage Renal Disease (ESRD) and require dialysis or transplantation (CDC 2019). Because ESRD qualifies patients for Medicare regardless of age, much of the related expenditures are funded with taxpayer money. Total Medicare expenditures for CKD and ESRD amount to $114 billion or 20% of the annual Medicare budget (CMS 2020). Patients who do not obtain a transplant receive dialysis therapy for five to 10 years before dying prematurely. Reducing the kidney shortage would have large benefits for taxpayers and society. Recent estimates indicate that each kidney transplant generates $146,000 in savings to taxpayers and $1.1 million net welfare gain to society compared to dialysis (Held et al. 2016). Increasing the number of kidney donations from living donors would reduce the shortage. However, considerable financial burdens exist that limit living kidney donation. Existing estimates suggest that living kidney donors face up to $38,000 of direct and indirect costs from the donation, and only a fraction of these costs is currently reimbursed (McCormick et al. 2019).
Policy Recommendation
Remove all financial disincentives to living kidney donation. Specifically, a comprehensive set of measures would include: (a) reimbursement of all direct costs (including lost earnings and dependent care) to all living kidney donors; (b) providing donors with a comprehensive insurance “packet” including short-term life insurance, disability insurance, and health insurance for long-term medical care; and (c) providing a refundable tax credit to offset the inconvenience, pain, and anxiety associated with the surgical procedure. While the National Organ Transplant Act (NOTA) prohibits payments to organ donors, it does not preclude providing compensation that covers the costs associated with donating. The notion that financial disincentives should be removed appears to enjoy broad support in the transplant community (although there is some disagreement about precisely what types of costs should be reimbursable), and recent survey studies indicate that compensation to living kidney donors provided by a government agency would enjoy robust support from the public.
Potential Savings
A comprehensive program that eliminates all financial disincentives to living kidney donation could save between $1 billion and $3 billion per year in Medicare spending (approximately 0.5% of Medicare spending). Total societal gains could exceed $7 billion per year.
Background
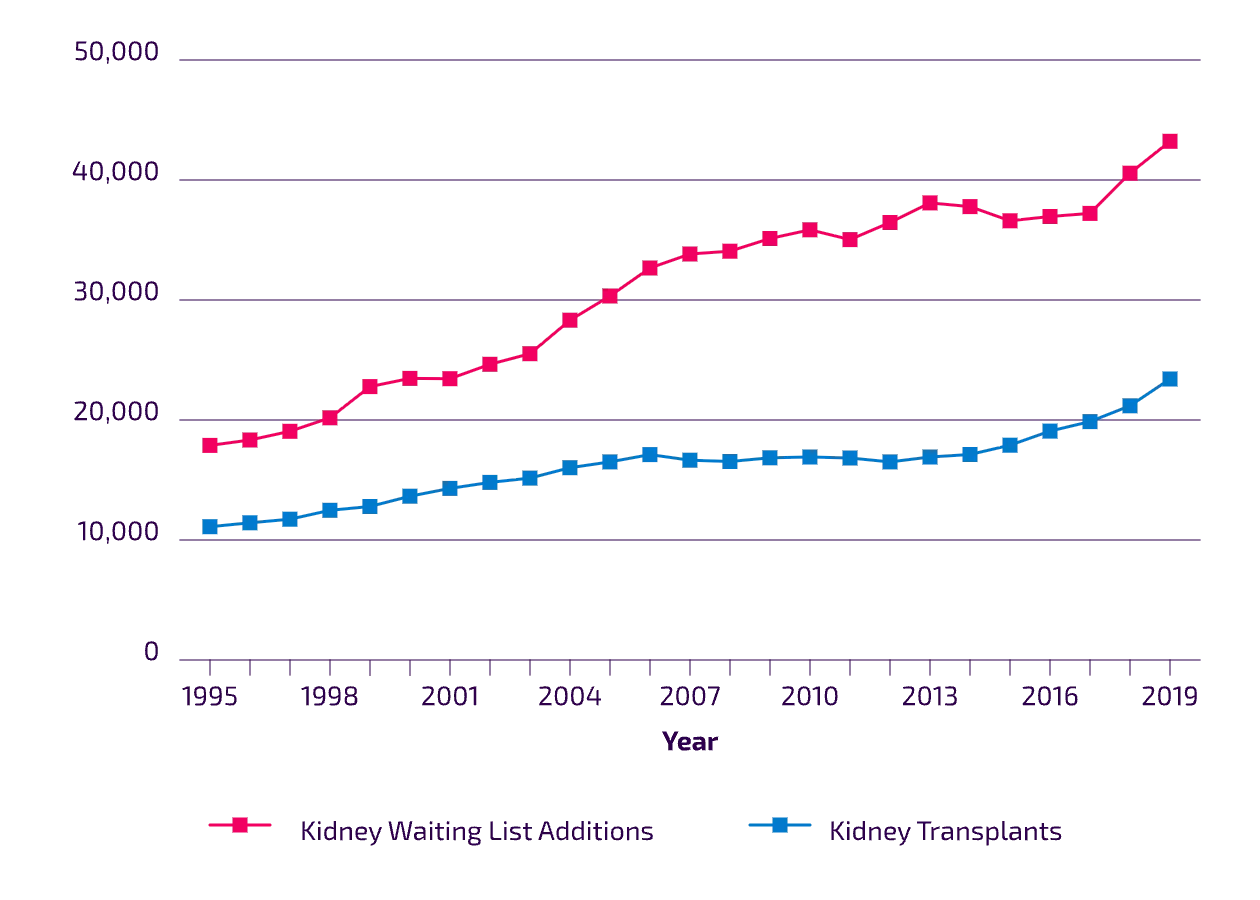
An estimated 37 million Americans suffer from CKD, and about 726,000 have ESRD and require dialysis or transplantation (CDC 2019). Each year, approximately 125,000 new cases of ESRD are reported. In 2019, 41,105 patients were added to the kidney transplant waiting list, and 23,401 transplants were performed (OPTN 2020).1 As shown in Figure 1, the imbalance between waiting list additions and transplants is a persistent feature of the US system. Over time, the chronic shortage of kidneys for transplantation resulted in a waiting list that currently includes approximately 92,000 patients with an average waiting time of four to five years (OPTN 2020).2
Figure 1: Additions to the Kidney Waiting List and Kidney Transplants (1995–2019)
The human and financial cost of the kidney shortage is large. ESRD patients who receive a transplant enjoy longer life expectancy and better quality of life compared to patients who remain on dialysis. According to recent estimates (Held et al. 2016), the median ESRD patient on the waiting list has an expected remaining lifetime of 12.3 years. In contrast, waitlist patients who receive a transplant can expect to live 19.3 years. The typical ESRD patient on dialysis visits a medical facility three times a week for three- to five-hour sessions. In addition to the inconvenience and disruption of daily life, dialysis causes significant physical discomfort and is debilitating (many patients stop working and go on disability when they go on dialysis), and it is associated with increased morbidity, hospitalization, and depression (Kimmel et al. 2008; Weisbord 2016; Offer et al. 2007).
In contrast, patients who receive a kidney transplant typically experience higher quality of life overall compared to dialysis, albeit lower compared to the general population. (Patients who receive a new organ must take immunosuppressive drugs that reduce the risk of organ rejection but weaken the immune system.) Estimates of quality of life range from 0.45 to 0.60 for dialysis patients and from 0.65 to 0.82 for patients who received a kidney transplant (Cook and Krawiec 2014; Held et al. 2016). Recent estimates indicate that transplant patients enjoy 6.5 additional quality-adjusted life-years (QALYs) compared to remaining on dialysis, with each kidney transplant generating net welfare gains for society of about $1.1 million (Held et al. 2016).3 In 2019, 3,264 patients died while on the transplant waiting list, and 3,233 were removed from the waiting list because they became too sick to receive a transplant (OPTN 2020). Thus, the societal cost of the kidney shortage is in the order of $7 billion annually. The cost is much greater if we consider that a large number of ESRD patients who are not on the kidney transplant waiting list could actually benefit from receiving a transplant.4
In addition to being an inferior treatment medically, dialysis is also more expensive than transplantation. According to the 2019 United States Renal Data System report (Saran et al. 2019), hemodialysis expenditures amount to $91,795 per patient per year (PPPY),5 whereas the PPPY cost for transplant patients is $35,817. Thus, an additional benefit from transplants is the reduction in medical expenditures. Because ESRD qualifies patients for Medicare regardless of age, much of the related expenditures are funded with taxpayer money.6 Held et al. (2016) estimate the present discounted value of taxpayer savings from each kidney transplant to be about $146,000.
Evidence Base
Of the 23,401 kidney transplants performed in 2019, 16,534 were from deceased donors and 6,867 from living donors (see Figure 2). Although additional donations from deceased persons would be beneficial, even recovering 100% of medically suitable organs from deceased patients would not be sufficient to fill the gap between need and supply.7 Thus, increasing the number of living kidney donations is important to solving the kidney shortage problem.8
Most people have two kidneys but can function normally with only one, which makes living kidney donation possible. Donating a kidney requires undergoing a surgical procedure (nephrectomy). Prior to the surgery, the prospective donor undergoes medical testing to ensure that the person is sufficiently healthy to donate; psychological and financial evaluations are also performed.9 The surgery is performed under general anesthesia and takes three to five hours. In most cases, four to six weeks recovery time is required before kidney donors can return to normal activities.
Figure 2: Kidney Transplants, Total and by Source (1988–2019)
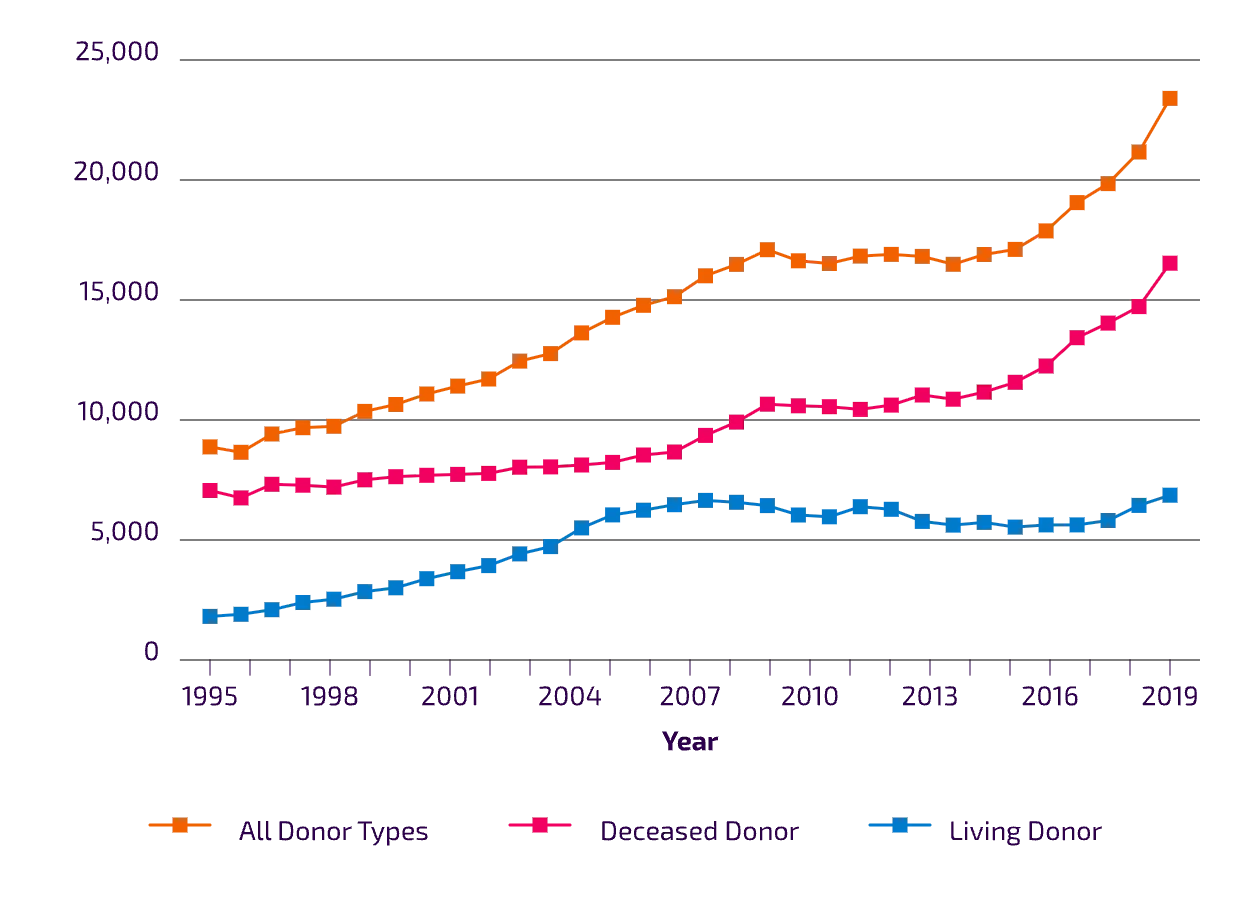
NOTA of 1984 prohibits donors from receiving “valuable consideration” for organs to be used for transplantation (42 U.S. Code § 274e). Yet, financial burdens have been identified as a critical barrier to living kidney donation. The medical costs of the donation are covered by the organ recipient’s health insurance. However, there are additional sources of direct and indirect costs associated with living organ donation that are currently not (or only partially) reimbursed and that, as such, constitute financial disincentives. Prospective cohort studies have identified a set of direct and indirect costs from donating a kidney (Przech et al. 2018; Rodrigue et al. 2016), and a few studies provided quantitative estimates of costs for typical living donors in the US (Gaston et al. 2006; Becker and Elias 2007; Delmonico et al. 2015; McCormick et al. 2019). Most recently, McCormick et al. (2019) presented an especially comprehensive account of the various sources of direct and indirect costs faced by living kidney donors and quantified them either directly or by referring to existing studies. Below is a list of the main costs that have been highlighted by the studies mentioned above:
Travel and Subsistence: Estimates of living kidney donors’ travel costs to the transplant center and subsistence costs (e.g., lodging, meals) range from about $2,000 (Przech et al. 2018) to $3,122 (McCormick et al. 2019). In 2006, the National Living Donor Assistance Center (NLDAC) was established with the purpose of implementing a living organ donor reimbursement program funded by the Health Resources and Services Administration (HRSA). NLDAC reimburses donors and their accompanying persons for travel costs and other qualifying subsistence expenses (lodging and meals), subject to a threshold of income eligibility for the donor and the recipient of the organ. The income threshold was set at 300% of the Health and Human Services’ (HHS) Poverty Guidelines until September 2020, when a new rule issued by HRSA revised the threshold to 350% of the HHS Poverty Guidelines (42 CFR Part 121 2020). Moreover, reimbursement can only be provided when payment cannot reasonably be covered from other sources such as state programs, insurance policies, and the recipient of the organ. Between September 2014 and January 2019, NLDAC approved 2,900 applications out of 3,300 applications received (42 CFR Part 121 2019). In 2018, NLDAC approved 1,055 applications (the average reimbursement was $1,934); for comparison, in that year 6,442 transplants from living donors were performed.
Loss of Earnings: Donors who are unable to work while they prepare for and recover from the surgery suffer a loss of income due to lost earnings. Estimates of lost income range from about $3,800 (Przech et al. 2018) to about $5,000 (Rodrigue et al. 2016; McCormick et al. 2019). McCormick et al. also included in their calculations the opportunity cost from the use of sick days and vacation days that could have been used for other purposes. Until September 2020, NLDAC could reimburse eligible donors only for travel and subsistence costs. The new final rule issued by HRSA in September 2020 expanded the scope of reimbursable expenses incurred by living organ donors to include up to four weeks of lost wages associated with the surgery and recovery time, subject to the same eligibility conditions described above for travel and subsistence expenses.
Unpaid Work and Dependent Care: A considerable proportion of kidney donors report being unable to perform household activities and being unable to care for dependents (young children or elderly relatives). In a prospective cohort study of Canadian living kidney donors, Przech et al. (2018) estimated median costs of lost home productivity and household and dependent care of about 6,000 Canadian dollars (about $4,900 US). Until recently, such costs were not reimbursable by NLDAC. The new final rule issued by HRSA in September 2020 expanded the scope of reimbursable expenses to include child-care and elder-care expenses. Again, the eligibility requirements are that the household income of donor and recipient do not exceed 350% of the HHS Poverty Guidelines, and that payment of those expenses cannot be covered by other specified sources of reimbursement.
Risks from Surgery: The kidney removal surgery is associated with a set of risks including adverse reactions to anesthesia, hospital-acquired infections, deep venous thrombosis, and other conditions. Drawing on figures from Gaston et al. (2006) and McCormick et al. (2019), we estimate this cost to be about $6,500. Moreover, the surgery carries a small but not insignificant risk of dying.10 Estimates of this cost range from about $2,000 (McCormick et al. 2019) to approximately $7,000 (Becker and Elias 2007), depending on assumptions made on the value of a statistical life.
Long-Term Health Risks from Kidney Removal: Although donating a kidney is not associated with higher long-term risk of death, kidney donors face a higher risk of developing ESRD, and women donors face a higher risk of preeclampsia (O’Keeffe et al. 2018).11 McCormick et al. (2019) quantify the expected discounted value of these risks at about $8,000, and Becker and Elias (2007) give a value of approximately $10,000.
Other Costs: Additional costs include the inconvenience, pain, and anxiety associated with the nephrectomy. Gaston et al. (2006) quantify these costs at about $5,000. Moreover, giving a kidney to anyone now precludes the donor from donating to a friend or relative who might need a kidney in the future. McCormick et al. (2019) quantify this opportunity cost to be about $8,000.
Although the total actual cost of donating a kidney varies in the population of donors depending on individual circumstances, the available estimates suggest that these costs are substantial for many donors. Becker and Elias (2007) estimate costs ranging from $10,000 to $35,000 (depending on assumptions of the value of a statistical life and of quality-of-life deterioration due to the nephrectomy); Gaston et al. (2006) estimate costs of up to $33,000. A recent, comprehensive analysis performed by McCormick et al. (2019) suggests that the typical American living kidney donor faces a $38,000 cost from the donation.
Policy Recommendation
For many Americans with ESRD, the alternative to a kidney transplant—dialysis—leaves them with poorer health outcomes and lower life expectancy, and costs taxpayers money. Increasing the number of transplants would improve health for tens of thousands of patients annually and reduce Medicare spending. Because the full demand for kidneys cannot be met with organs from deceased donors, increasing living kidney donations is important. However, as discussed above, living kidney donors incur direct and indirect costs from the donation, and the fact that only a fraction of those costs is currently reimbursed helps explain why the quantity of kidneys supplied is insufficient to meet the need.
Removing all financial disincentives to living kidney donation has the potential to increase the number of transplants and, over time, eliminate the waiting list. While NOTA prohibits payments to organ donors, it does not preclude providing compensation that covers the costs associated with donating. The discussion and references mentioned above suggest a set of measures that could achieve this policy goal:
- Implement a system of reimbursement of all direct costs including travel and subsistence, lost earnings, and dependent care regardless of donor and recipient income levels. This objective could be achieved with a robust expansion of the NLDAC program.
- Provide donors with short-term life insurance, disability insurance, and health insurance for long-term medical care (protecting donors from short-term post-surgical complications as well as long-term health issues). To achieve this, a comprehensive insurance “packet” could be designed and offered to all kidney donors.
- Provide a refundable tax credit to offset the inconvenience, pain, and anxiety associated with the surgical procedure (Gaston et al. 2006 suggest either a $5,000 direct payment or a $10,000 tax deduction). This proposed measure would require a congressional amendment to NOTA.
Acceptability and Implementation
Removing financial barriers to make organ donation “financially neutral” for the donor (i.e., donors should not be made financially worse off by the donation) is a policy goal that appears to enjoy widespread support in the transplant community (Gaston et al. 2006; Delmonico et al. 2015; Salomon et al. 2015; Tushla et al. 2015; Hays et al. 2016). However, there is disagreement about the ethicality of providing reimbursement for costs associated with subjective factors such as pain and risk (Danovitch et al. 2020).
Fully removing disincentives for all living organ donors is likely consistent with NOTA. Elements (1) and (2) of the policy proposal above could potentially be accomplished with regulatory change. The recent reform introduced with HRSA’s September 2020 final rule made several steps in the right direction. The definition of allowable expenses that can be reimbursed to low-income donors now includes lost wages and dependent care expenses, in addition to travel and subsistence expenses. Moreover, the rule clarified that non-directed living organ donors are also eligible beneficiaries of the NLDAC program.12 However, as illustrated above, there are additional disincentives that are not addressed by the program. Also, the fact that the household income of both donor and recipient must be under 350% of the poverty threshold, and that the program provides reimbursement only if the expenses cannot be reasonably expected to be paid by other programs or by the organ recipient, are features that limit the potential effects on the supply of kidneys. For element (3), instead, a congressional amendment to NOTA would likely be required. The experimental survey of Elias, Lacetera, and Macis (2019) conducted on a representative sample of US residents suggests that tax deductions and refundable tax credits (and even direct payments) provided by a government agency would be perceived as ethically acceptable by the general public if they resulted in more transplants and lives saved.
Potential Savings
Removing all disincentives by compensating donors for the full direct and indirect costs of giving a kidney could have a sharp effect on supply. Becker and Elias (2007) argue that compensating donors to make them indifferent between donating or not would cause the supply curve to become highly elastic, thereby generating enough kidneys to completely satisfy the need.13 In that scenario, Held et al. (2016) suggest that savings for taxpayers would be in the order of $12 billion annually (equivalent to 2% of the annual Medicare budget). Estimates described in McCormick et al. (2019) are more conservative but still substantial. They suggest that reimbursing donors for all expenses (up to $38,000) could increase kidney transplants by 12,500 per year, which would imply savings for Medicare and Medicaid of $1.8 billion annually (savings would range between $1.0 and $2.7 billion per year, depending on the responsiveness of potential donors to the removal of disincentives).
In contrast, compensating donors for only part of their costs would have a more limited effect on supply. For instance, several US states provide paid or unpaid leave to state employees who are organ donors,14 and some offer state tax deductions or credits to offset donors’ costs. However, a few recent empirical studies found that these policies did not have a meaningful effect on organ donations (Boulware et al. 2008; Venkataramani et al. 2012; Lacetera, Macis, and Stith 2014).15 Bilgel and Galle (2015), however, estimate that tax incentive legislation increased living unrelated kidney donations by 52% in the state of New York. More recently, Schnier et al. (2018) studied how the number of donations changed when the NLDAC began reimbursing travel expenses during the process of donation. Those authors found a 14% increase in donations as a result of an average travel reimbursement of about $2,800. However, it is difficult to extrapolate these results to a different set of policies or target populations. Ultimately, pilot randomized trials should be conducted to estimate the effects of various possible forms of reimbursement and compensation provided to living organ donors in the US.16, 17 It will also be important to evaluate the effects of the September 2020 NLDAC expansion measures described above.
Addendum
This addendum was prepared by the Health Care Affordability Lab at Yale.
The financial burden of donating remains a barrier to living kidney donation. Among applicants to the federal National Living Donor Assistance Center, 72% said that aid would make donation possible (Mathur et al. 2024). Policy has begun moving toward lowering the financial burden of donating an organ.
In February 2026, Congress enacted the Honor Our Living Donors (HOLD) Act, which bars the federal donor reimbursement program—run by the National Living Donor Assistance Center—from counting the recipient’s income when determining a donor’s eligibility for aid. HRSA’s proposed rules to implement the law would still means-test donors and cap reimbursement at $6,000 (HRSA 2026). New York has gone even further, reimbursing eligible donors up to $14,000 (New York State Department of Health 2025).
The projected savings of going beyond cost reimbursement may be larger than the brief’s initial estimates suggested. McCormick et al. 2022 estimated that compensating donors by roughly $77,000 each, a payment set above donors’ actual costs, could attract enough kidneys to provide transplants to approximately 47,000 more patients each year. The authors caution that these are rough projections rather than precise estimates. They also estimated that each transplant would produce about $1.5 million in benefits for the recipient and caregiver and about $1.2 million in savings from avoided dialysis.
However, recent trials suggest that partial assistance would have only a limited effect on kidney supply. In one trial, offering donors up to $1,500 or $3,000 in lost-wage reimbursement did not significantly increase donor evaluations or transplants within one year, though an exploratory analysis with longer follow-up suggested a possible effect (Rodrigue et al. 2026). In another trial, financial assistance paired with social-worker support similarly produced no significant increase in donor activity, though participants rarely used the assistance offered (Boulware et al. 2021). Both programs covered only a narrow share of the costs donors face, leaving much of the financial penalty of donation intact. Per Boulware et al., the lack of effect may stem from low awareness and uptake of the assistance program, as well as a lack of coverage for other costs that deter donors, like lost wages. Rodrigue et al. suggest their null effect could stem from partial aid being insufficient to offset donors’ economic barriers; social and interpersonal barriers, like emotional readiness and relationship dynamics, may also play a role.
Several pending bills aim to further reduce the financial barriers to donation. The End Kidney Deaths Act would give a refundable tax credit—$10,000 a year for five years—to non-directed donors, meaning those who give a kidney to a stranger on the waiting list rather than to a specific person they know. The Expanding Support for Living Donors Act and Living Donor Protection Act would broaden reimbursement and strengthen insurance and job protections, respectively. The Living Donor Protection Act advanced through the Senate HELP Committee in February 2026.


More Briefs
$12-$24B
Expanding Site-Neutral Payments in Medicare and Addressing Anticompetitive Vertical Integration of Physicians
