

Improving Auto-Assignment in Medicaid Managed Care

Issue Summary
The Medicaid program accounts for approximately 28% of state budgets, covers 77 million people, and represents 16% of US health care spending. Approximately 70% of Medicaid enrollees are now enrolled in Medicaid managed care plans operated by private firms. There is a growing body of work illustrating that insurance plan design (including the design of Medicaid managed care plans) can have a substantial influence on enrollee health, satisfaction, and spending. In particular, health plan networks can be structured so as to meaningfully reduce health spending without harming quality or satisfaction. Currently, a significant portion of Medicaid managed care plan enrollees do not make an active choice to enroll in a particular plan, and instead are assigned to a plan by the state via a process known as “auto-assignment.” Assuming auto-assignment rates are stable over the next decade, states will auto-assign approximately 25 million Medicaid enrollees to their respective Medicaid managed care plans during this time. This creates an opportunity to develop novel methods for auto-assignment that capitalize on differences in plan quality and networks to reduce Medicaid spending without adversely impacting enrollee health or satisfaction.
Policy Recommendation
We encourage states to adopt smart defaults when auto-assigning Medicaid enrollees to managed care plans. States have an opportunity to leverage auto-assignment as a tool to better understand the efficiency of the plans in their market and then as a tool to steer enrollees into plans that constrain spending without reducing enrollee satisfaction or health. For example, research suggests that auto-assigning Medicaid enrollees into narrower network plans that include their usual providers can lower cost without harming enrollee satisfaction or health.
Potential Savings
Based on evidence from one of the largest Medicaid managed care programs in the United States, we estimate the adoption of smarter defaults would lower spending in Medicaid by approximately 1%. This translates to $3.7 to $9.2 billion in annual savings, or a 0.10% to 0.24% reduction in national health expenditures in the US.
Background
The Medicaid program provides health insurance coverage to over 77 million individuals and accounts for approximately 16% of US health spending at a cost of $613.5 billion per year. A significant portion of Medicaid costs are borne by states, with Medicaid program costs now accounting for approximately 28.7% of state governments’ expenditures. The vast majority of states now rely primarily on risk-based managed care plans operated by private firms to provide benefits to Medicaid enrollees. At present, approximately 70% of Medicaid enrollees are in a risk-bearing managed care plan.
There is a growing body of work suggesting that insurance plans can have a substantial impact on enrollee health spending and outcomes. These effects can be on a similar scale as—or larger in magnitude than—the effects of demand-side interventions like patient copayments or deductibles. Much of the academic research suggests that the differences in enrollee outcomes across insurance plans are the result of differences in the networks of participating providers across plans. Recent evidence from New York State, for example, illustrates that if enrollees are assigned to narrower network plans that include their usual providers, health spending can be reduced by 2% to 5% without adversely impacting enrollee satisfaction or health.
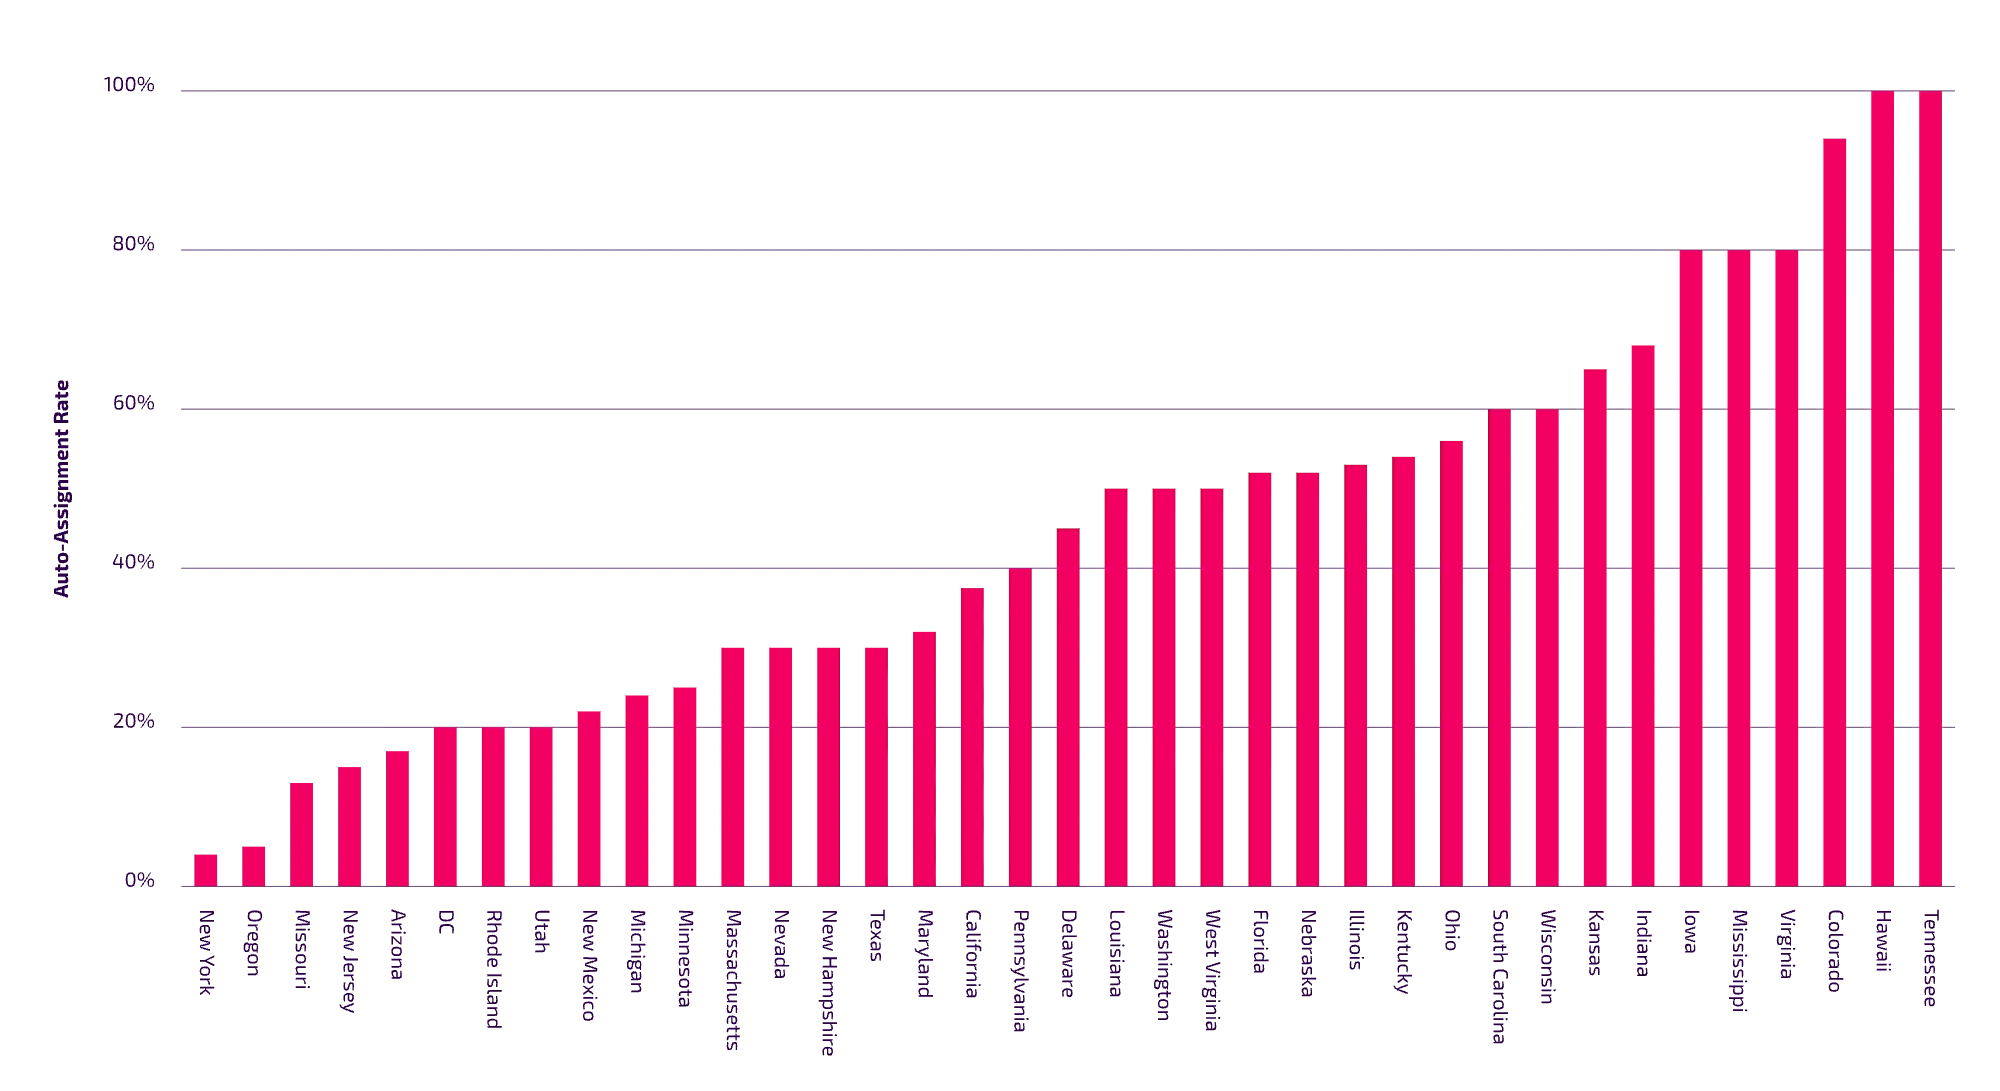
A large share of Medicaid enrollees do not make an active choice to enroll in a particular Medicaid managed care plan. As we illustrate in Figure 1, in some states, all of the state’s Medicaid enrollees are auto-assigned to a plan. The best estimates are that nationwide, 25 million individuals will need to be auto-assigned to a Medicaid managed care plan over the next decade. As a result, there is significant scope for state Medicaid programs to structure auto-assignment to plans in ways that make their Medicaid programs more efficient.
Figure 1. Auto-Assignment Rate by State
Evidence Base
The Effects of Medicaid Managed Care Plans on Enrollee Outcomes and Health Spending
There is significant variation in how states currently auto-assign Medicaid enrollees to managed care plans, reflecting the lack of a clear consensus on best practice. It is common for states to include logic that keeps family members together or assigns enrollees to plans they’ve previously chosen. However, many auto-assignees are allocated to plans via algorithms that attribute them at random to qualifying plans. In some states, the allocation of auto-assignees is equal across plans, but in others plans with larger market shares receive more (or fewer) auto-assignees. While the diversity of approaches likely reflects, in part, the competing priorities of policy makers in different states, the lack of a clear best practice indicates that substantial potential exists to improve the efficiency of the Medicaid program with smarter default policies.
When states randomly assign Medicaid enrollees to plans, they offer researchers the opportunity to identify how Medicaid managed care plans causally impact enrollee outcomes and health spending. Here, academic research suggests that the lowest-spending Medicaid managed care plans can reduce health spending by over 30% (Geruso, Layton, and Wallace 2020). Unfortunately, in some instances, these lower-spending plans constrain cost by reducing enrollees’ utilization of both needed and unneeded services, rather than simply eliminating the use of wasteful services.
However, recent research suggests that narrower network plans could reduce enrollee spending without harming consumer satisfaction or increasing the likelihood of adverse health events. Wallace (2020) studies auto-assignment in New York and finds that enrollment in a narrower network plan can reduce enrollee spending by approximately 10%. Although these reductions are driven by decreases in the quantity of care consumed, including some preventive services, they do not appear to increase the likelihood of adverse health events. While narrower networks do reduce enrollee satisfaction, the evidence suggests this effect can be mitigated by ensuring that enrollees retain access to their preferred providers.
The experience in New York suggests that the potential for auto-assignment to influence outcomes is substantial and that there are opportunities to lower cost without sacrificing enrollee satisfaction. Relative to a policy that randomly assigns enrollees to plans, a smarter default for auto-assignees could reduce spending by nearly 3% while maintaining enrollee satisfaction. These savings come via shifting enrollees to narrower network plans (to reduce spending) that include the enrollees’ usual sources of care (which increases satisfaction).
Policy Recommendation
Because Medicaid managed care is mandatory in most states, but many Medicaid enrollees do not actively choose a managed care plan within a designated choice period, policy makers need a method to auto-assign enrollees to plans. Whenever possible, policy makers should structure these auto-assignments in ways that improve health, maintain enrollee satisfaction, and reduce health spending. Early evidence suggests that one mechanism to lower spending without adversely impacting quality or enrollee satisfaction is to auto-assign enrollees to narrower network plans that include the enrollees’ usual providers within their networks. Going forward, more work should be done to determine how to most efficiently match enrollees to plans in ways that increase the efficiency of state Medicaid programs.
Potential Savings
Based on evidence from one of the largest state Medicaid programs in the United States, we estimate that the adoption of smarter defaults in state auto-assignment algorithms could lower total spending in Medicaid by approximately 1%. This translates to approximately $3.7 to $9.2 billion in annual savings, or a 0.10% to 0.24% reduction in current national health expenditures in the US. The range in spending comes from different assumptions about the potential cost savings that could be achieved via smart defaults. The more conservative projection assumes that smarter defaults will only leverage the comparative advantage of plans, reassigning enrollees to maximize efficiency without changing plan market shares. The more aggressive projections relax the constraint that plan shares be maintained. Without this constraint, the projected savings are larger, but so is the potential for reshaping the market in unintended ways. Hence, states may initially prefer a more incremental approach.
Addendum
This addendum was prepared by the Health Care Affordability Lab at Yale.
Smarter auto-assignment defaults—assigning Medicaid beneficiaries to the best matched insurance plan for then, when beneficiaries themselves don’t make a choice—remain a major but underused opportunity to improve the efficiency of Medicaid managed care programs. From the latest available data in 2015, roughly 45 percent of beneficiaries in the median state did not choose their own managed care plan and were instead assigned by the state. However, only ten states at minimum incorporate quality into auto-assignment, and none explicitly assign based on plan costs (KFF 2022). States therefore continue to have substantial room to reward plans that provide high-quality care at lower cost (Shepard and Wallace 2026).
A key design challenge is that conventional measures of plan performance may reflect differences in who enrolls rather than how well plans perform. A randomized study of Louisiana Medicaid found that spending differences across plans were more than twice as large among beneficiaries who chose their plans than among those randomly assigned, and standard risk adjustment did little to close the gap (Wallace et al. 2022). Smart auto-assignment therefore cannot rely on existing plan rankings alone. States need measures that separate true plan performance from enrollee selection so they can reliably identify high-quality, low-cost plans.
More recent evidence shows that losing an established provider can disrupt care, suggesting that auto-assignment should consider keeping beneficiaries with their usual providers wherever possible, especially for the chronically ill. When a Medicaid managed care beneficiary’s primary provider left the plan’s network, the share of beneficiaries with a primary care visit fell by about 5 percent over the next year (Staiger 2022). The effect was larger for beneficiaries with chronic conditions, whose primary care use fell by 4.2 percentage points and whose likelihood of hospitalization rose by 2.1 percentage points. A separate study of a statewide reshuffling of children with asthma across Medicaid plans found that those who were forced to change plans were less likely to have a routine outpatient visit (a 2.1-percentage-point reduction per quarter compared to those who stayed in their plan) (Piwnica-Worms et al. 2021). However, the disruption had no measurable effect on asthma care quality, emergency visits, or hospitalizations.
Recent CMS rulemaking, though not directly implementing auto-assignment, will give states more comparable information on plan access and quality that can support smarter assignment decisions. A 2024 rule requires states to set and monitor appointment wait times, verify provider directory accuracy, and publish standardized plan quality ratings, with major requirements phasing in from 2027 through 2028 (CMS 2024). Separately, CMS issued guidance to strengthen continuity of care when beneficiaries move between plans by advising states to preserve existing providers, treatments, prescriptions, and prior authorizations (CMS 2023).
A pending federal bill would extend smart auto-assignment nationwide. The Better Care, Better Cost Act, introduced by Representative Craig Goldman in June 2026, would require states beginning in 2028 to score Medicaid managed care plans on spending, health outcomes, and member satisfaction and use those scores when assigning beneficiaries who do not choose a plan (Better Care, Better Cost Act 2026).



