

Less Is More: Structuring Choice for Health Insurance Plans

Issue Summary
Insurance product choice is a central feature of health insurance markets in the United States. Individuals face a choice over plans in commercial health insurance markets, as well as over whether or not to enroll in Medicare Advantage, across Medicare Advantage plans and Medicare Part D plans, and across Medicaid managed care plans. This expansion of choice raises a number of issues. Foremost among them is the question of whether consumers can adequately choose from a variety of complicated health insurance options. A number of studies illustrate that consumers don’t appear to choose plans that are best for them financially—in the extreme, even making “dominated choices” that would be worse no matter what their medical spending turns out to be.
This past literature is broadly critical of unfettered choice across insurance options but offers some important lessons for how to structure that choice. Improving individuals’ choices over insurance plans can lower their premiums (choosing equally good plans with lower premiums), lower their out-of-pocket costs (choosing plans best suited to their future spending), and increase competition in insurance markets (by making it harder for poor-quality plans to persist).
Policy Recommendation
Policy-makers and employers can take a number of steps to improve the environment where individuals select insurance plans. This will help individuals make better product choices. Recommendations include:
- Restricting the choice sets individuals face (while preserving choices) by eliminating the lowest-performing plans that are bad for most beneficiaries;
- Pairing decision support tools with agents who help individuals select products; and
- Introducing defaults when the defaults do not force large switching costs (e.g., they do not require changes in provider networks). Defaults also can be effective when individuals enter insurance markets for the first time.
Potential Savings
The savings for individuals from making more appropriate choices over their insurance products could be substantial. In the context of Medicare Part D, researchers find that only about 15% of seniors choose the lowest-cost option in their choice set and that the typical senior could save around one third of their costs by choosing that best option (Abaluck and Gruber 2011, 2016; Heiss et al. 2013). These findings extend to Medicare Advantage, where the average enrollee in a large insurance exchange leaves $1,300 on the table when choosing their plan (Gruber et al. 2020). In the employer-sponsored market, many employees make “dominated choices”; that is, they choose plans where, regardless of what they end up spending, they could have done better, and they lose substantial amounts of money (24% of chosen plan premiums) by not avoiding dominated plans (Bhargava et al. 2017). Approximately 45 million individuals are enrolled in a Medicare Part D plan, approximately 22 million are enrolled in a Medicare Advantage plan, and 158 million have an employer-sponsored plan (Cubanski et al. 2019; Freed 2020; Kaiser Family Foundation 2019). To give a back-of-the-envelope scale of the possible savings, if each individual saved $100 per year from improved choice, this would result in $4.5 billion in savings for those in Medicare Part D, $2.2 billion for those in Medicare Advantage plans, $15.8 billion for those with employer-sponsored plans, and $22.5 billion in aggregate per year. These savings represent approximately 1% of total Medicare spending and 1.3% of total commercial health insurance spending.
Background
Insurance product choice is a central feature of health insurance markets in the United States. Approximately 50% of US residents get their coverage from an employer, and 58% of those offered employer-sponsored insurance have a choice of insurance plans (Kaiser Family Foundation 2019). Those who buy private insurance under the state and federal exchanges established by the Affordable Care Act (ACA) had an average of 20 plans per county being offered on the exchanges in 2016 (Abaluck and Gruber 2019). The Medicare program provides insurance coverage to approximately 60 million elderly and disabled Americans (Kaiser Family Foundation 2020). Within the Medicare program, enrollees have a choice between the traditional Medicare program and an average of 21 “Medicare Advantage” plans that provide a private alternative (Jacobson et al. 2015). In the Medicare prescription drug program, which was added in 2006, enrollees have a choice of more than 40 private prescription drug insurance plans (Kaiser Family Foundation 2020). The lowest-income Americans who are insured through Medicaid typically can choose from a variety of managed care plans for their coverage, with 290 total managed care organizations operating in 38 states and Washington, DC, and an average choice set of eight plans per state (Kaiser Family Foundation 2018, Abaluck and Gruber 2019).
This expansion of choice raises a number of issues, as reviewed in Gruber (2017). Foremost among them is the question of whether consumers can adequately choose from a variety of complicated health insurance options. A number of studies illustrate that consumers don’t appear to choose plans that are best for them financially—in the extreme, even making “dominated choices” that would be worse no matter what their medical spending turns out to be (Bhargava et al. 2017). This past literature is broadly critical of unfettered choice across insurance options but offers some important lessons for how to structure that choice. In this note, we discuss those important lessons.
Evidence Base
Lesson #1: Individuals Struggle When Choosing Insurance Plans
A wide variety of studies have examined choice in government plans such as Part D and Medicare Advantage, in the ACA exchanges, and in employer insurance. The broadly shared conclusion is that choices are poor and that individuals leave a lot of money on the table through these poor choices.
The studies that examine this question typically proceed by comparing the total enrollee spending, including both premiums and out-of-pocket medical costs, in the chosen plan versus what they would spend if enrolled in other plans in their “choice set” (the set of plans available). To measure these counterfactual costs in other plans, researchers use the observed spending in the previous year and ask: Given past spending, what would be the expected costs for enrollees in each plan they could choose?1 They then compute the “foregone savings” from the individual’s choice relative to the lowest-cost option in the choice set.
The findings of these studies are striking and consistent. In the context of Medicare Part D, researchers find that only about 15% of seniors choose the lowest-cost option in their choice set and that the typical senior could save around one third of their costs by choosing that best option (Abaluck and Gruber 2011, 2016; Heiss et al. 2013). These findings extend to Medicare Advantage, where the average enrollee in a large insurance exchange leaves $1,300 on the table when choosing their plan (Gruber et al. 2020).
Perhaps most striking is evidence from employer-sponsored insurance. Numerous studies document large foregone savings in this setting. But most damning is the evidence that many employees make “dominated choices”; that is, they choose plans where, regardless of what they end up spending, they could have done better, and they lose substantial amounts of money (24% of chosen plan premiums) by not avoiding dominated plans (Bhargava et al. 2017).
What is driving these poor choices? Three key phenomena have been identified:
- Enrollees are highly inertial and don’t change plans nearly enough when either their medical spending changes or better new options are added to the choice set.
- Enrollees pay too much attention to differences across plans in the regular monthly premium that they pay and not enough attention to the differences in the out-of-pocket medical costs they will face with each choice.
- To the extent that enrollees pay attention to medical spending, they focus on general plan characteristics (does the plan have a high hospital deductible?) and not to the plan characteristics that impact their own expected spending (because the person is unlikely to use the hospital).
These struggles with choosing the best-matched insurance plan highlight the savings available from improving individuals’ choices.
Lesson #2: Structuring Choices Can Improve Decision-Making
The first public exchange was the Massachusetts Connector. At its inception in 2006, the Connector specified three tiers (gold, silver, bronze) with defined levels of insurance generosity (or “actuarial value”) (Ericson et al. 2017). Within each tier, insurance companies were completely free to set their cost-sharing structure, and this varied widely, resulting in 25 different plan structures across six different companies (with additional differences across companies in network restrictions). Due to public dissatisfaction with the confusing array of choices, in 2010 the Connector decided to structure the set of choices much more tightly, allowing only seven different options for plan structure (although networks still differed widely).
Research on this change shows that it substantially impacted choices. Prior to the reform, consumers overwhelmingly chose low-premium plans. After the reform, they were more likely to choose plans with more generous coverage (Ericson and Starc 2016).
Recommendation: Limiting the structure of plans that can be offered can lead individuals to be less likely to make suboptimal choices.
Lesson #3: Fewer Options Are Better (If Competition Is Maintained)
One way to prevent bad choices is to limit the number of choices available to enrollees, specifically by removing bad options. A large body of literature has shown that individuals are more reluctant to participate in markets where there are a large number of choices, perhaps because they feel overwhelmed. Recent work on the employer insurance options available to school district employees in Oregon shows that individuals also make worse choices when the choice set is larger (Abaluck and Gruber 2019). Employees faced a range of insurance options that all included the same physician network but differed in the generosity of the financial coverage across plans, ranging from a plan with fairly complete coverage to a high-deductible option.
Overall, there were large foregone savings that averaged more than $500 per employee. More striking, however, is the variation in that foregone savings by choice set size, shown in Figure 1.2 Foregone savings rise from $352 in plans with two choices to $1,118 in plans with seven choices (Abaluck and Gruber 2019). And this does not just reflect the best option getting better; the plans in which beneficiaries actually enrolled cost more in larger choice sets. Enrollees end up enrolled in less suitable plans when there are more options.
Figure 1: Forgone Savings by Choice Set Size
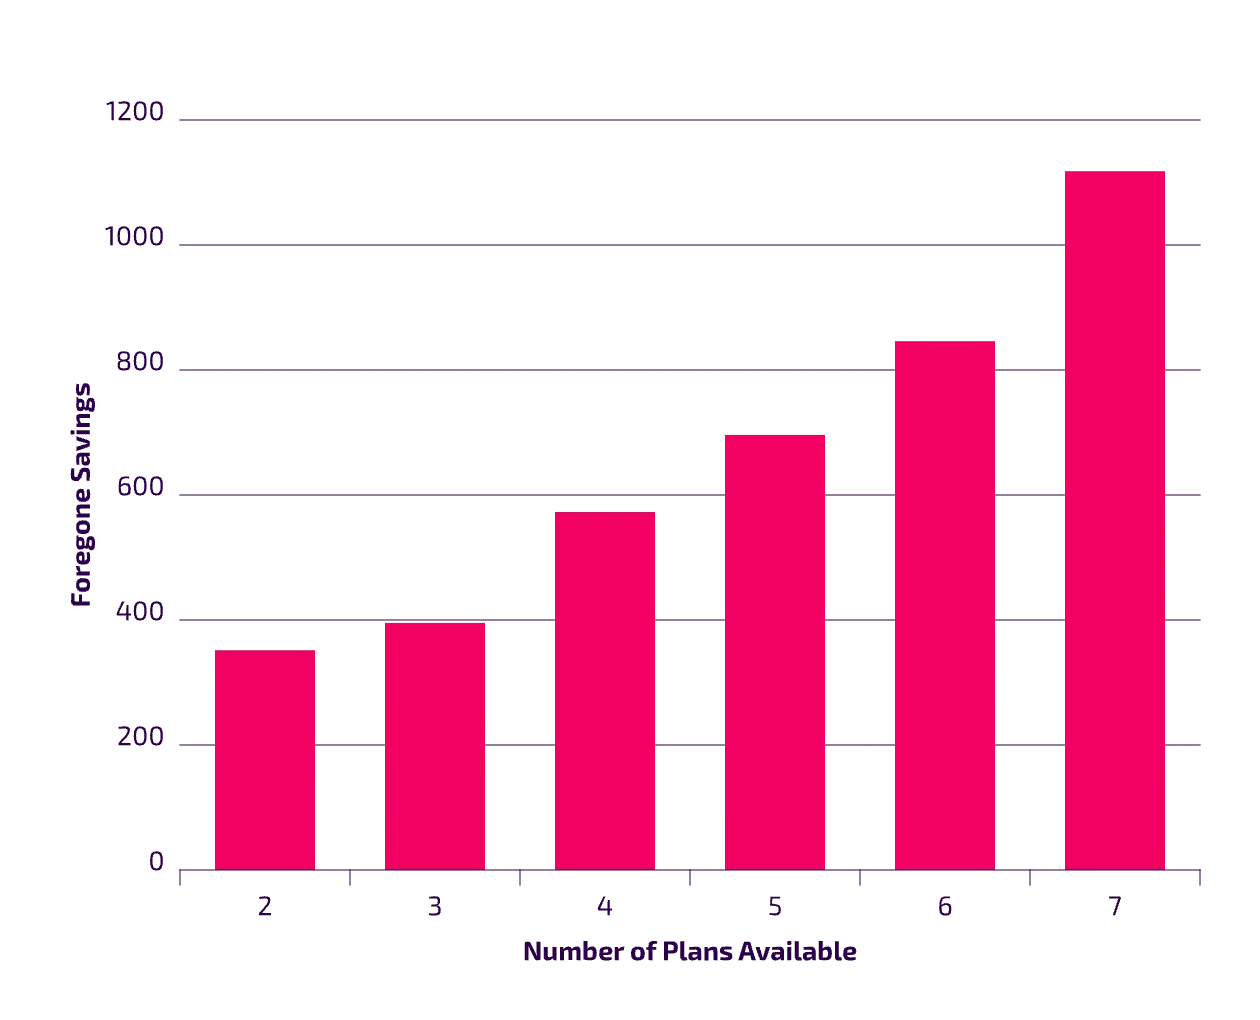
Why are fewer choices better? A typical explanation is “choice overload”: individuals facing too many choices do a bad job choosing. But, in fact, that isn’t the explanation—individuals seem to do an equally bad job choosing regardless of the number of insurance options that are available (Abaluck and Gruber 2019). Rather, the problem seems to be with the set of available plans. When administrators allow choice from more plans, they include plans which are unsuitable for many beneficiaries. This leads to worse choices.
Given this, one might ask why the optimal outcome isn’t always to just offer one option. But this discussion has ignored the supply side of the equation—with only one option, there will be no competition, and as a result, premiums might be too high. In principle, this problem could be resolved by having competition be the single option offered to enrollees—that is, plans could bid to be the single option. But this has the consequence that, once an insurer is entrenched as an option, individuals will be reticent to start over year after year, so there won’t be fair competition between the inside insurer and potential outside options.
Recommendation: Restricting the number of plans on offer in a market can make selecting a plan easier. Policy-makers should consider a first-stage bidding process to be able to offer plans on an exchange.
Lesson #4: In Choosing Plans, Focus on What Is Best on Average
Even with a more limited set of plan choices, administrators still need to decide which plans to offer. Administrators face tension between meeting the diverse demands of their constituents and trying to reduce the foregone savings that arise with a wide variety of choices. Research findings suggest a simple resolution to this problem: choose the plans that are best on average, and don’t add additional plans just because they meet the needs of a small subset of enrollees.
Consider an administrator that is offering a few common options and is deciding whether to offer a new option that is particularly valuable for some enrollees. In a perfect world, by adding that plan, the administrator meets the needs of those employees without making anyone else worse off. However, when that plan is added, many of those who might actually benefit won’t choose it—and others for whom it might be worse may choose it.
Recommendation: Administrators should focus on adding insurance plan choices that are better, on average, than existing options rather than just adding plans that appeal to small segments of the market.
Lesson #5: Agents Help a Little, and Decision Support Helps a Little, but Putting Them Together Helps a Lot
There are two approaches to improving choices given the available choice set. One is to provide skilled agents who can help enrollees choose, and the other is to provide decision support tools that enrollees can use when enrolling. Studies of these tools suggest that each may induce a small improvement separately, but can pay big dividends when combined (Ericson et al. 2017).
Several studies have investigated how decision support tools impact enrollee choices. The main finding is that such tools are not widely used by enrollees, even when available and use is encouraged (Abaluck and Gruber 2016).
Medicare Advantage enrollees through exchanges often have agents available to assist with choices. One study found that enrollees using agents don’t appear to choose much better than those who aren’t using agents in other contexts (Gruber et al. 2020). However, that same study then provided those agents with a decision support tool and mandated that they use it to assist enrollees. Choices improved substantially, with a one-third reduction in foregone savings for enrollees (Gruber et al. 2020).
Recommendation: Collectively, the evidence suggests that an effective approach for improving choices would be to offer access to skilled agents who are equipped with decision support software.
Lesson #6: Defaults Can Improve Choice, but Use with Caution
As noted above, many beneficiaries are inertial. Evidence suggests that much of this inertia arises due to inattention—consumers do not actively make a choice and are defaulted into whatever option they previously had (Abaluck and Adams 2017). This suggests that changing defaults could be a powerful tool to direct consumers into more appropriate plans (Handel and Kolstad 2015).
Research suggests that better defaults can lead to better choices; however, defaults must be used with care. In many environments, consumers have real costs of switching plans; the cost savings from an alternative plan may not be worth it if consumers must also switch care providers.
Defaults can most effectively be used in settings where these switching costs are likely to be small and where the benefits of better defaults are large. For example, for general medical insurance plans, one might only consider defaulting beneficiaries into plans where all of their existing providers remain in network.
For prescription drug insurance plans, there is no concern that consumers will have to switch providers, but there may be costs of learning to navigate a new plan (e.g., coordinating mail-order drug delivery). Research suggests that these costs can be substantial, but defaults can still lead to better choices, especially if they are focused on the beneficiaries with the largest benefits. For example, rather than defaulting all beneficiaries, one might default only beneficiaries who stand to save at least $500 by choosing an alternative plan since the costs of navigating a new plan are unlikely to be that large.
Recommendation: Policy-makers should consider defaulting individuals into good options when they enter a new market. Likewise, defaulting individuals into good plans can be effective when the switch to a new plan does not have high costs (e.g., a change in a provider network or a change in the way prescriptions are filled).
Addendum
This addendum was prepared by the Health Care Affordability Lab at Yale.
Choosing among health plans continues to be a challenge for consumers. Recent research reinforces how consumers are strongly drawn to their default option rather than actively choosing a plan that works best for them. In Medicare Part D, over 70% of enrollees choose the same drug plan as their partner—a “social default” (Gross et al. 2025). Even among couples whose health needs clearly differ, well over half still choose the same plan.
Other recent work tests solutions. In a field study and series of experiments simulating an online exchange, researchers found that two design choices work best in combination to nudge enrollees towards better plans: ordering plans by predicted total spending (rather than premiums alone) and showing a short initial list of the best options (Dellaert et al. 2024). Using administrative data from California’s individual market, other work identifies sources of consumer inertia and find that hassle costs and inattention cost consumers about $1,790 per household per year (Drake et al. 2022). That amounts to roughly half the median household premium. Interventions that reduce these costs, such as informational nudges, better default plan algorithms, and simpler choice presentation, would improve consumer welfare.
On the policy side, federal regulators moved to structure marketplace choice after the brief’s publication. In 2023, HealthCare.gov required insurers to offer standardized plan designs, and beginning in 2024, it phased in limits on the number of non-standardized plans an insurer could offer (Pollitz et al. 2023; Chu et al. 2021). Some state-based marketplaces have pursued similar approaches and limited the number of plan offerings (Pollitz et al. 2023).
More recently, federal policy has shifted in the other direction. The 2025 Marketplace Integrity and Affordability final rule shortened the open enrollment window and paused the year-round low-income special enrollment period, reducing the time and support available for plan selection (CMS 2025). In May 2026, CMS finalized its Notice of Benefit and Payment Parameters for 2027, which removes the requirement that insurers offer standardized plans and permits new plan types, including multi-year catastrophic plans. These changes widen the range of options consumers must sort through and could offset recent efforts to simplify plan choice (CMS 2026).



