

Paying for Biologic PADs in Medicare Part B

Issue Summary
Medicare spending on physician-administered drugs (PADs) continues to increase substantially and is being driven in large part by higher prices. PADs are covered under Medicare Part B for Medicare enrollees and under the medical benefit for most commercial enrollees. Under the current structure, the physician chooses a version of the drug to purchase, holds the inventory, and then prescribes and administers it. When administered, the physician receives a payment, which is typically equal to the cost to acquire the drug charged by the manufacturer plus a specified markup. In the US, each biologic PAD and each individual biosimilar PAD has its own reimbursement amount based on its distinct billing code, known as its J-code. As a result, current procurement policy for biologic PADs under Medicare Part B avoids all competitive market forces. It does not create any incentive to compete on price; rather, it rewards higher-priced drugs by permitting firms to set any price they want Medicare to pay and giving no incentive to physicians to avoid high-priced drugs. Compounding the problem, many commercial insurers follow Medicare reimbursement rules for PADs. The J-code regulations entirely defeat the purpose of biosimilar entry, which was designed to create price competition for old biologic drugs in the way that generic drugs lower prices in the pharmacy channel. With R&D pipelines filled with biologic drugs, it’s imperative to modify the design of Medicare J-codes to generate competition amongst manufacturers of biologic PADs and incentivize physicians to prescribe lower-cost biosimilars.
Policy Recommendation
This brief proposes changing the design of Medicare J-codes for PADs so that there is a single J-code for each molecule: the reference biologic and all of its biosimilar versions. Physicians should then be compensated a fixed amount for administering any product in the J-code group. The fixed amount could be the price of the least-costly alternative in the J-code plus 5%, or $500, whichever is smaller.
Potential Savings
Biologic PADs are a large and growing share of Medicare. Moreover, many commercial plans follow Medicare payment schemes. Under conservative assumptions, this policy would save $2 billion per year, and it might save as much as $7.5 billion per year, which is approximately 1% of Medicare spending.
Background
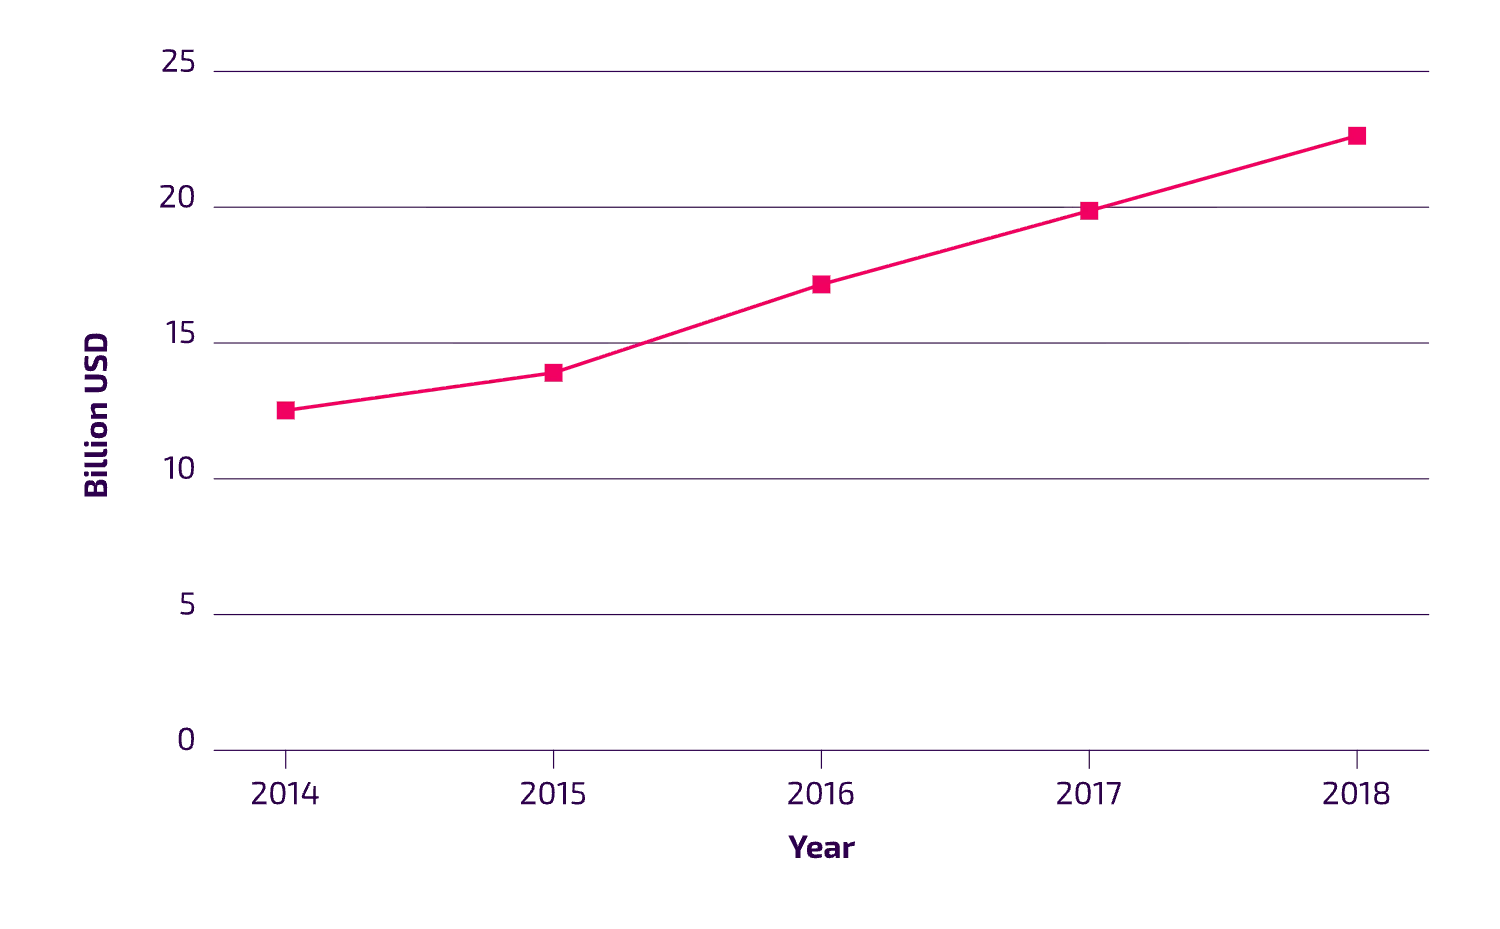
PADs are treatments such as injections or infusions that are administered by physicians in an outpatient setting (e.g., doctor’s office). Medicare covers PADs under Part B and, analogously, commercial health insurance plans typically cover PADs as part of the medical benefit. Two thirds of Medicare Part B drug spending is on biologic drugs (MedPAC 2017). In 2018, total Medicare PAD spending on biologics was $22.63 billion (FDA 2020; CMS 2020).
Spending on PADs is growing much faster than spending on self-administered drugs and represents the largest growth in spending for professional services (HCCI 2019, 16).1 Medicare alone spent $32 billion on PADs in 2017, and, on average, expenditure grew by 9.7% annually between 2009 and 2015 (MedPAC 2018). This increase in spending was driven primarily by price rather than utilization; the average payment per Part B drug increased on average by 6.6% annually (MedPAC 2018). These steep price increases can be attributed to the way Medicare currently procures PADs. Physician practices or hospital outpatient departments purchase PADs from group purchasing organizations, distributors, wholesalers, or the manufacturers themselves (Ginsburg, Brandt, and Lieberman 2019).2 Physicians choose a version of the drug to buy, stock the drug, and incur inventory costs. Unlike most small-molecule drugs, many PADs cost thousands of dollars (MedPAC 2015, 66) and are perishable (County of Suffolk v. Abbott Laboratories), so they have high inventory costs. Physicians then dispense the drug and receive a payment from a patient’s medical insurer. Many commercial insurers follow Medicare reimbursement rules for PADs, so the Medicare rules take on outsized importance in terms of influencing the pricing behavior of manufacturers.3
Table 1: Estimated Spending on Biologic PADs by Medicare Part B
Evidence Base
Medicare pays the physician an amount known as the Average Sales Price (ASP) plus 6%.4 The ASP is calculated as the volume-weighted sales to all purchasers (with some exceptions5) across all drugs categorized under the same billing code, known as a J-code. Specifically, manufacturers submit their ASPs for all forms and sizes of the drug, and the Centers for Medicare and Medicaid Services (CMS) aggregates a volume-weighted ASP for each J-code. Physicians are paid the ASP from two quarters before the patient’s visit plus 6% as a profit margin. For a biosimilar, the ASP is based on its J-code and the 6% markup is based on the reference biologic’s ASP. Commercial insurers use the Medicare rate as a benchmark for negotiation, though they often pay a markup higher than 6%.
Herein lies the key issue: under the current Medicare rules, each biologic and each biosimilar receives its own distinct J-code and corresponding reimbursement price from Medicare.6 From the manufacturer’s perspective, the J-code reimbursement scheme with one manufacturer in it is a cost-plus contract. This creates no price competition. Instead, the manufacturer of a drug freely chooses a launch list price or raises its existing list price as much as it desires, and then sells to physician groups and hospital outpatient departments whose demand does not fall in response to the higher prices. The current system results in the government paying the price the manufacturer chooses, whatever the level of that price and regardless of the amount of competition in the market.
In addition, because physicians are reimbursed for their acquisition costs, the level of the manufacturer’s price does not affect their demand. Physicians have no incentive to consider equally effective but lower-priced alternative drugs such as biosimilars. Physicians are constrained only by their patients; to the degree patients cannot afford, and do not pay, the 20% coinsurance that applies to the drug, the physician would be disincentivized to administer it. However, 34% of fee-for-service Medicare (i.e., original Medicare) beneficiaries have supplemental coverage, and another 31% of beneficiaries have Medicare Advantage, both of which further insulate patients from costs (AHIP 2018). As a result, only a fraction of Medicare enrollees are responsible for the 20% coinsurance and could potentially exhibit elastic demand.
In short, current Medicare regulations insulate biologics from price competition. The way the government procures these drugs incentivizes manufacturers of both biologics and biosimilars to maintain high list prices. These prices are then paid by commercial customers as well and raise the cost of health care for all Americans.
Policy Recommendation
This brief proposes changing the design of Medicare J-codes for PADs so that there is a single J-code for each molecule: the reference biologic and all of its biosimilar versions. Physicians should then be compensated a fixed amount for administering any product in the J-code group. The fixed amount could be the price of the least-costly alternative in the J-code plus 5%, or $500, whichever is smaller.
Under this scheme, when multiple manufacturers have a drug paid by the same J-code, each will face downward pressure on its price because customers—the physicians—will be paid a fixed amount regardless of which drug in the group they choose to buy. The single J-code creates a financial incentive for the provider to purchase from the least-expensive manufacturer in the J-code. A physician or hospital will increase its margin by purchasing a drug in the J-code group with a lower price. They are also likely to notice if buying a particular drug leaves them with a loss; for example, because its price is above the fixed reimbursement amount. Therefore, the J-code creates an incentive for manufacturers in the same J-code to compete for the business of physicians by lowering their prices. Sharing a J-code is a way for Medicare to create price competition between manufacturers of the same drugs and to generate awareness by physicians for potentially lower-cost alternatives.
Studies have shown that when reference products compete with biosimilars, there is downward pressure on price. Scott Morton et al. (2018) estimate that average market prices decrease by 3.5 percentage points per year after biosimilar entry. For each additional distributor, there is an additional 2.4 percentage point decrease in price. These estimates are reflective of the experience of European countries plus Australia, where, in aggregate, a 30% reduction in savings is commonplace. Norway was able to achieve a 70% reduction in biologic spending from introduction of a biosimilar (Mack 2015).7
Potential Savings
To estimate the potential cost savings of biologic competition in the US, this brief takes all biologic products (reference products and biosimilars) licensed by the Food and Drug Administration (FDA) as of March 2020.8 By merging these biologics with spending data from Medicare Part B in 2018, estimated cost savings are simulated by applying a percentage discount in price to biologics with existing biosimilars in 2020, and then secondly to all biologics that have been on the market for a certain number of years. This calculation is intended to represent the steady-state value of the J-code reform in an environment with biosimilar entry.
Table 2, using a range of these back-of-the-envelope calculations, shows that potential cost savings are large and range from approximately $1 billion to $7.5 billion. For example, Scenario 2 assumes that all biosimilars that are currently approved by the FDA enter the market and compete against reference biologic products. As is common in Europe, it is conservatively assumed that the biologics facing competition see a 30% decrease in spending. Overall, this leads to savings of $1.94 billion, which represents an 8.6% decrease in total spending by Medicare Part B on biologic PADs. Under this same scenario, if it is assumed that biologics facing competition experience a 50% decrease in spending, savings is estimated to be $3.24 billion, which represents a 14.3% decrease in spending by Medicare Part B on biologic PADs. Scenario 3 shows savings from a 30% decrease in price applied to all biologics that have been on the market for more than 20 years. This results in savings of $1.38 billion. Likewise, assuming a 50% decrease in price for all biologics on the market for more than 20 years results in savings of $2.29 billion, this represents a 10.1% reduction in total spending by Medicare Part B on biologic PADs. Each scenario assessed if biologics facing competition experience a 30%, 50%, and 70% decrease in spending, respectively. Based on the resulting savings calculations, under conservative assumptions this policy would save around $2 billion per year, and it might save as much as $7.5 billion per year, which is approximately 1% of Medicare spending.
Table 2: Simulated Savings on Biologic PADs by Medicare Part B
These savings estimates likely understate the full impact of this change in policy. As more biologics and biosimilars are developed, approved, and competitively priced within a J-code, physicians may consider therapeutic alternatives across molecules. This consideration will result in further competition amongst manufacturers of biologic PADs and corresponding savings.
Addendum
This addendum was prepared by the Health Care Affordability Lab at Yale.
Fee-for-service Medicare Part B drug spending reached $54 billion in 2023, growing 9.4% per year on average between 2009 and 2023 (unadjusted for inflation)—with biologics making up 16 of the top 20 drugs by 2023 spending (MedPAC 2025). In 2023, eight reference biologics in Part B faced competition from 27 biosimilars. Across these eight molecules—a reference biologic plus all its biosimilars—39% of treated traditional Medicare beneficiaries used a biosimilar, according to the Office of the Assistant Secretary for Planning and Evaluation (ASPE 2025). ASPE estimates that biosimilar competition reduced Medicare Part B drug spending by $12.9 billion between 2018 and 2023—about 31% below what it would have been without competition. Those savings came partly from beneficiaries shifting to lower-cost biosimilars and partly from several reference-product manufacturers cutting their own prices sharply to retain market share (ASPE 2025).
Medicare Part B continues to pay for physician-administered drugs through billing codes known as J-codes, each carrying its own payment rate based on the product’s average sales price. Medicare assigns the reference biologic and each of its biosimilars a separate J-code, so every product in a molecule is reimbursed at its own rate rather than at a single rate for the group. Because these products are close therapeutic substitutes billed under different codes, Medicare cannot pay for all of them at the lowest price available in the group. For three of the eight studied by ASPE—Epogen, Lucentis, and Neulasta—the average biosimilar is priced higher than the reference product, yet each is still paid at its own rate; for others, the reference product costs more than twice its biosimilars yet still draws meaningful volume at that higher rate (ASPE 2025).
Congress has since adjusted what Part B pays for biosimilars, though without changing the underlying code structure. To modestly encourage biosimilar use, the Inflation Reduction Act of 2022 temporarily raised the Part B add-on payment for qualifying biosimilars from 6% to 8% of the reference biologic's average sales price (ASP) for five years beginning October 2022 (ASPE 2025).
ASPE and the HHS Office of Inspector General (OIG) have each modeled a payment policy, called a least costly alternative (LCA), that closely parallels this brief's proposal. Under an LCA policy, Medicare would pay the same rate for a reference product and all its biosimilars, set at the price of the lowest-cost option in the group, regardless of which version a provider administers. Both estimates point in the same direction. HHS OIG estimates that an LCA policy would have reduced Part B and enrollee spending by $419 million (9%) in 2021 (HHS OIG 2023). ASPE estimates $3.1 billion in additional Medicare savings between 2018 and 2023, including roughly $950 million in 2023 alone (ASPE 2025). Advancing such a policy would require congressional action, since CMS has stated that Section 1847A of the Social Security Act limits its ability to change Part B drug payment policy on its own (HHS OIG 2023).
Biosimilar competition has lowered Part B spending since this brief was published, but substantial savings remain unrealized under the current code structure. Capturing them, as both ASPE and OIG model, would require moving to a single payment rate per molecule.


More Briefs
1.3%-5.3%
Ending Pay-for-Delay Patent Litigation Settlements in the Pharmaceutical Industry
